




Yes, Medicare covers ambulance rides, but only when the ride is medically necessary and goes to the nearest appropriate facility. Medicare Part B covers ground ambulance transportation, and after the Part B deductible you pay 20% of the Medicare-approved amount. In 2026 that deductible is $283. Air ambulance is covered only in narrow situations. Below, we walk through what qualifies, what you will owe, and the mistakes that lead to surprise bills.
TL;DR
- Original Medicare (Part B) covers medically necessary ground ambulance trips to or from a hospital, critical access hospital, rural emergency hospital, or skilled nursing facility.
- You pay 20% of the Medicare-approved amount after the $283 Part B deductible (2026). There is no yearly out-of-pocket cap in Original Medicare unless you add supplemental coverage.
- Medicare pays only to the nearest appropriate facility. Choosing a farther one for personal preference can leave you paying the difference.
- Non-emergency rides, such as recurring dialysis trips, need strict proof of medical necessity. A doctor’s order alone is not a guarantee.
- Air ambulance is covered only when ground transport is too slow or cannot reach you and rapid transport is medically necessary.
Table of Contents
- What Medicare covers: the basics
- What you will pay
- Emergency rides
- Air ambulance
- Non-emergency ambulance transport
- Ambulance coverage under different plan types
- How to avoid a surprise ambulance bill
- Our perspective
- Reviewing your coverage with us
- FAQ
- Sources
What Medicare covers: the basics
Medicare treats an ambulance as a medical service, not a taxi. Part B (Medical Insurance) covers ambulance services to or from a hospital, critical access hospital, rural emergency hospital, or skilled nursing facility. That list matters. A ride from your home to a doctor’s office, a dentist, or a pharmacy is not on it.
The test Medicare applies is simple to state and harder to meet in practice: other transportation, such as a car or taxi, would endanger your health. Think chest pain, stroke symptoms, a serious fall with a suspected fracture, or severe bleeding. If a family member could safely drive you, Medicare is unlikely to call the ambulance necessary.
The federal rule behind this is 42 CFR 410.40. It also sets requirements for the ambulance vehicle and crew, which is why the company you ride with has to be an enrolled Medicare supplier. If you want a refresher on how Part B works in general, our Part B guide for 2026 covers premiums, the deductible and what else it pays for.
What you will pay
Here is the cost structure for Original Medicare in 2026:
| Item | Your cost |
|---|---|
| Part B annual deductible | $283 |
| After the deductible | 20% of the Medicare-approved amount |
| Medicare-approved amount | Set by Medicare’s fee schedule, not by the ambulance company’s bill |
The deductible and coinsurance figures come from Medicare.gov. Two things make the math less friendly than it looks.
First, the 20% has no ceiling. As Medicare explains, there is no yearly limit on what you pay out of pocket unless you have supplemental coverage such as a Medigap policy. One long transport can mean a meaningful bill, and repeated trips add up.
Second, the 20% is calculated on the approved amount. If you are in the deductible phase, say it is early in the year and you have not used Part B yet, you pay the first $283 of approved charges yourself before the 20% starts.
A worked example
Suppose you have not met your deductible and the Medicare-approved amount for a ride is $1,000. You would pay the $283 deductible, then 20% of the remaining $717, which is $143.40. Your total would be $426.40, and Medicare would pay the rest. This is an illustration with a made-up approved amount, not a quote. Actual approved amounts vary by location and the level of service, and Medicare publishes its ambulance fee schedule for billers.
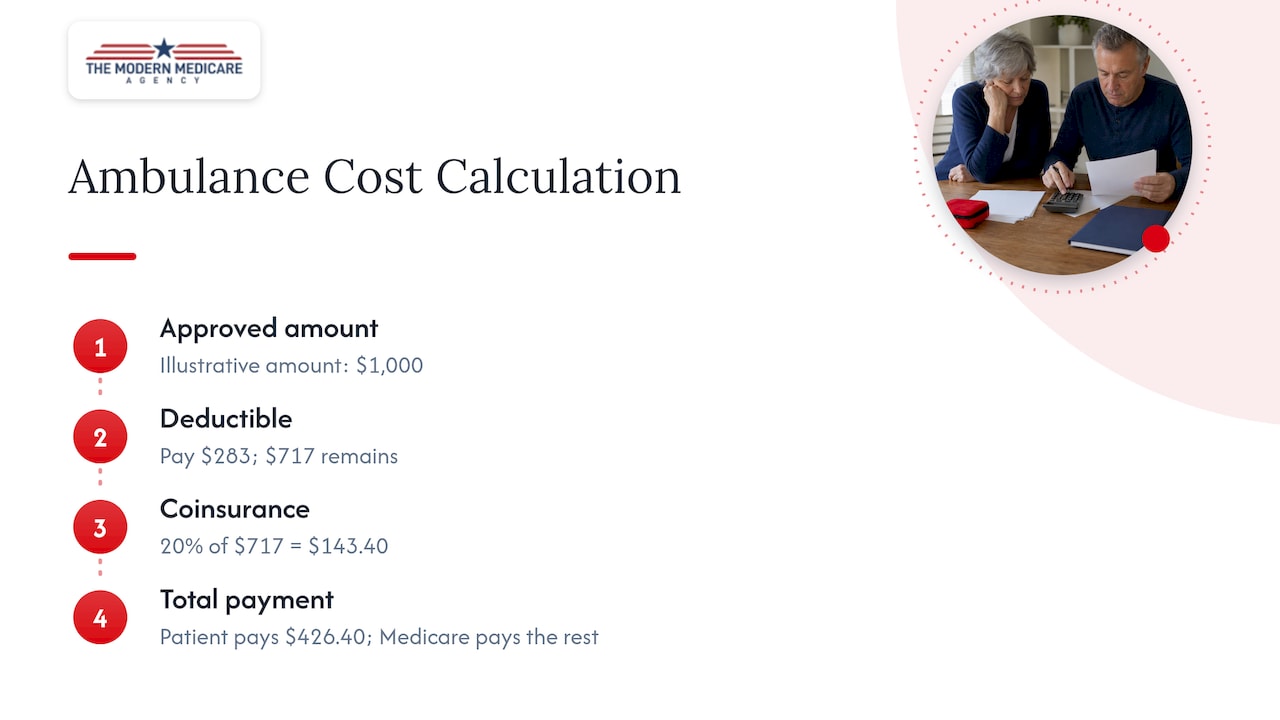
If you have already met the deductible that year, the same ride would cost you $200.
Emergency rides
In a true emergency, you should call 911. Medicare covers emergency ambulance services when your health is in serious danger and other transportation could endanger you. You do not need prior approval, and nobody expects you to weigh coverage rules while someone is having a heart attack.
What matters afterward is where the ambulance takes you.
The “nearest appropriate facility” rule
A common misconception is that any ride you call 911 for is fully covered. Medicare pays for transport to the nearest facility that can treat your condition. If you choose a hospital farther away, for example because your cardiologist practices there, Medicare will pay only what the trip to the nearest appropriate facility would have cost. You owe the difference.
“Appropriate” is about capability, not convenience. If the closest hospital has no stroke center or trauma unit and yours requires one, a farther hospital that does can be the nearest appropriate one. Paramedics often make that call on scene. When you can, ask the crew where they are taking you and why.
When Part A is involved
Most ambulance claims go through Part B. In some cases, such as when you are transferred between facilities as part of an inpatient stay, the transport may be bundled into the hospital’s payment instead. The relevant CMS guidance covers transport that is packaged into an institutional service. If a bill arrives that seems to double up, ask the hospital’s billing office which payer was charged.
Air ambulance
People search for air ambulance coverage because the bills are famously large. Medicare does cover it, but narrowly. In rare cases, when ground transport is too slow or cannot reach you, Medicare may cover an airplane or helicopter if immediate, rapid transport is medically necessary.
In practice that means remote areas, situations where traffic or terrain would delay care in a time-sensitive emergency, or a patient who needs a specialized facility that ground transport cannot reach in time. Convenience, preference, or a long drive alone do not qualify. The same nearest-appropriate-facility rule applies.

If you live in a rural area or travel often to remote places, ask yourself what happens if a flight is deemed not medically necessary. That is a question for your coverage review, and we return to it below.
Non-emergency ambulance transport
Non-emergency rides are where most denials happen. Medicare covers them only if your condition makes other transportation dangerous to your health. The regulation points to patients who are bed-confined, meaning they cannot get up, walk, or sit in a chair or wheelchair without assistance. Examples include a patient moving from a hospital to a skilled nursing facility who cannot sit upright safely.
A few points to know:
- A doctor’s order is evidence, not a voucher. CMS says plainly that an order does not guarantee payment. Medicare assesses medical necessity on its own, based on your condition at the time of the trip.
- Ask about the ABN. If an ambulance company thinks Medicare may not pay for a non-emergency trip, it is expected to give you an Advance Beneficiary Notice of Noncoverage. Signing it means you accept possible financial responsibility. Read it before you sign, and ask what the ride would cost if denied.
- Scrutiny is real. CMS reports a 13.2% improper payment rate for ambulance services, so providers document carefully and claims get reviewed.
Dialysis and other repeat trips
If you need scheduled, repeated transport, for dialysis or wound care for instance, there is a safeguard. Under the Repetitive, Scheduled Non-Emergent Ambulance Transport (RSNAT) program, you or your ambulance company can request prior authorization. You can use it before the fourth trip in a 30-day period, and the decision usually arrives within 7 calendar days.
The process is voluntary, but it is worth using. Without it, you risk learning after the fact that Medicare denied the claim and the full charge is yours. CMS describes the model as one that asks for approval before the service is furnished and before a claim is submitted. Standard coverage rules still apply, so approval confirms that the trip meets them; it does not loosen them.
If your issue is getting to appointments rather than medical danger, an ambulance is the wrong tool. Our pages on medical transportation services and the Medicare Advantage transportation benefit explain the alternatives.
Ambulance coverage under different plan types
Your options depend on how you get Medicare.
| Coverage | How ambulance costs work |
|---|---|
| Original Medicare only | Deductible, then 20% with no annual cap |
| Original Medicare + Medigap | Many Medigap plans are designed to help with the 20% coinsurance; benefits differ by plan letter, so check the plan’s outline |
| Medicare Advantage | Must cover what Original Medicare covers, but copays, networks and rules vary by plan |
The Medigap and Advantage rows are general descriptions. Standardized Medigap plans differ in which Part B costs they pay, so confirm the letter and the carrier before assuming the 20% is gone. With Advantage, the ambulance copay is listed in each plan’s Evidence of Coverage, and a flat copay for an emergency ride can be lower or higher than 20% depending on the plan and the approved amount. You can read more in our Medicare Advantage guide and Medigap comparison for 2026.
Urgent care sometimes comes up in the same conversation, since people wonder whether to ride an ambulance or drive to a clinic. Our breakdown of urgent care versus the emergency room under Medicare helps with that decision, though in a real emergency you should call 911.
How to avoid a surprise ambulance bill
- Know your plan before you need it. Check whether you have Original Medicare, Medigap, or Advantage, and look up the ambulance cost-sharing line now.
- In an emergency, let the crew decide the destination. If you want a different hospital, ask whether it is the nearest appropriate one and understand you may owe the difference.
- For non-emergency trips, ask the ambulance company before the ride. Ask whether they expect Medicare to pay and whether you will be asked to sign an ABN.
- For recurring trips, request prior authorization. Ask the provider about the RSNAT process before the fourth trip in 30 days.
- Read every Medicare Summary Notice. If a claim was denied, you have appeal rights. The denial notice explains the steps and deadlines, and 1-800-MEDICARE can point you to the right place.
- Compare a bill to the approved amount. If a supplier billed you for more than Medicare’s 20% share, call and ask why before paying.
Our perspective
Ambulance coverage is a good example of why we put education before enrollment. Most people assume Medicare handles an emergency ride in full. It handles most of it, but the 20% with no cap, the nearest-facility rule, and the medical necessity test are details nobody explains until a bill shows up.
When we review coverage with someone, we do not start with a plan name. We ask how they would pay for a few bad weeks: an ambulance ride, an ER stay, a transfer to rehab. For many people, the answer shows a gap that a Medigap plan or a well-chosen Advantage plan can close, and for others the current plan is already the right fit. As independent agents, we are not tied to one carrier, so we can say so either way.
We also see people who are unhappy with the coverage they have, usually because no one ever checked it against their health and where they live. A rural address changes the air ambulance question. A dialysis schedule changes the transport question. Those facts should drive the plan, not the other way around.
— Paul
Reviewing your coverage with us
If you are turning 65, leaving employer coverage, or just not sure your current plan would hold up in an emergency, we can compare your options with you. We are an independent agency, and we help with Medicare Supplement plans, Medicare Advantage and Part D, with annual coverage checkups and year-round support. You can also read our own explainers on Medicare ambulance services coverage and whether Medicare pays for ambulance rides. To start a conversation, visit paulbinsurance.com.
FAQ
Does Medicare cover an ambulance ride to the hospital?
Yes, if the ride is medically necessary and goes to the nearest appropriate facility. Part B covers it after the $283 deductible in 2026, and you pay 20% of the Medicare-approved amount. Medicare covers rides to or from hospitals, critical access hospitals, rural emergency hospitals and skilled nursing facilities.
How much is an ambulance ride with Medicare?
You pay the deductible if you have not met it, then 20% of the Medicare-approved amount. The dollar figure depends on the approved amount for your trip, which varies by location and service level. A Medigap plan or a Medicare Advantage plan can change what you owe.
Does Medicare cover air ambulance transport?
Sometimes. Medicare may cover a helicopter or airplane when ground transport is too slow or cannot reach you and rapid transport is medically necessary. If a ground ambulance would have been enough, the flight is unlikely to qualify.
Will Medicare pay if my doctor orders an ambulance?
Not automatically. A doctor’s order supports the claim, but Medicare decides medical necessity based on your condition at the time of transport. For non-emergency trips, ask the ambulance company whether you will be asked to sign an ABN.
Does Medicare cover an ambulance to a hospital I prefer that is farther away?
Only up to the cost of going to the nearest appropriate facility. You are responsible for the difference. Tell the crew your preference, but ask whether the closer hospital can treat your condition.
Sources
- Medicare.gov: Ambulance services coverage
- Medicare.gov: Medicare Coverage of Ambulance Services (PDF)
- Medicare.gov: What does Medicare cost?
- eCFR: 42 CFR 410.40, Coverage of ambulance services
- CMS: RSNAT Prior Authorization Model (MLN6805343)
- CMS: RSNAT Prior Authorization FAQ
- CMS: Ambulance Services compliance tips
- CMS: Ambulance program integrity payment model press release
- CMS: Transmittal R243BP on ambulance transport and institutional services
- CMS: Ambulance Fee Schedule


