



Medicare Beneficiary Rights: Fair Treatment, Privacy and Care

Medicare Beneficiary Rights: Fair Treatment, Privacy and Care

To understand your rights as a Medicare beneficiary, start with the basics: you’re entitled to fair treatment, privacy for your health information, access to your records, and a say in decisions about your care. These protections also matter when you choose or use a Medicare Advantage plan. Knowing what they cover can help you respond when questions or problems arise.

Medicare rules and plan documents can be difficult to untangle, especially when you’re also managing a care or coverage decision. You may be unsure what you can ask for, what information you can access, or how to raise a concern. Understanding your rights can make the next step clearer.

This guide explains your rights in plain language, including protections against unfair treatment, privacy and access to health records, safe care, and Medicare Advantage plan choices. It also explains where to turn for help understanding coverage or addressing a concern, so you can make informed decisions with greater confidence.

Key Takeaways

  • You can take part in care decisions, ask questions, and raise concerns about unfair treatment or unsafe care.
  • You generally have the right to access your health records and request copies of personal health information.
  • Medicare Advantage members can ask how their plan pays doctors and use the plan’s process to challenge coverage decisions.
  • Keep records of care or coverage concerns and explain the issue clearly when seeking help.
  • Independent Medicare guidance can help you understand plan choices, including Medicare Advantage, Medigap, and Part D.

Fair treatment and protection from discrimination

Fair treatment means receiving care without unethical treatment or discrimination. Medicare rights and protections help shield beneficiaries from unethical practices. In a hospital, fair treatment also means freedom from physical or mental abuse, corporal punishment, restraints, seclusion, coercion, discipline, and retaliation. A patient who experiences any of these can raise the concern as a grievance. The hospital must have a process for promptly resolving patient grievances, with time frames for review and response under 42 C.F.R. § 482.13(a)(2).

Informed decision-making means you can understand your care options and accept or refuse treatment. Under 42 C.F.R. § 482.13(b)(2), hospital patients have that right, but cannot demand medically unnecessary or inappropriate services. For example, you may ask a clinician to explain a proposed treatment before deciding. You may also refuse it. Ask about the expected benefits, risks, and alternatives so your choice reflects the information available to you.

Taking part in a care plan means helping shape how your hospital care is developed and carried out. Hospital patients have this right under 42 C.F.R. § 482.13(b)(1). Share your priorities and relevant information with the care team. If a plan changes, ask what changed and how that affects the next steps. A clear conversation can help you understand what the team recommends and make your preferences known.

An advance directive records your wishes for future health care decisions. Under 42 C.F.R. § 482.13(b)(3), hospital patients have the right to formulate one and have hospital staff and practitioners comply with it. Tell the hospital if you have an advance directive and ask how staff will include it in your care. This can help keep your stated preferences visible when decisions need to be made.

Provider choice under Original Medicare means you may use a qualified provider who participates in Medicare. Federal Medicare law says beneficiaries may obtain health services from any institution, agency, or person qualified to participate, under 42 U.S.C. § 1395a(a). People with Original Medicare can use any health care provider or specialist, or any Medicare-certified hospital that takes Medicare. Medicare Advantage plan rules differ, so check the plan’s network and coverage terms before arranging care.

A Medicare benefit period is the period used to track certain inpatient hospital and skilled nursing facility care. According to Centers for Medicare & Medicaid Services, a Medicare benefit period ends after 60 consecutive days without inpatient hospital or skilled nursing facility care. If you’re unsure how a benefit period affects your care, ask the hospital or Medicare to explain how your recent stays fit the rule.

How can a Medicare beneficiary file a complaint or grievance? Tell the hospital or plan what happened, when it happened, and what response you’re seeking. Hospitals must have a grievance process with review and response time frames, so ask how to submit your concern through that process.

Privacy and access to personal health information

Privacy means your health information should be kept confidential. Access means you can view or obtain copies of records about your care. Medicare beneficiaries generally have these rights for information held by health care providers who treat and bill Medicare, and by health plans that pay for their care. Hospital patients also have the right to confidential clinical records and access to their own records.

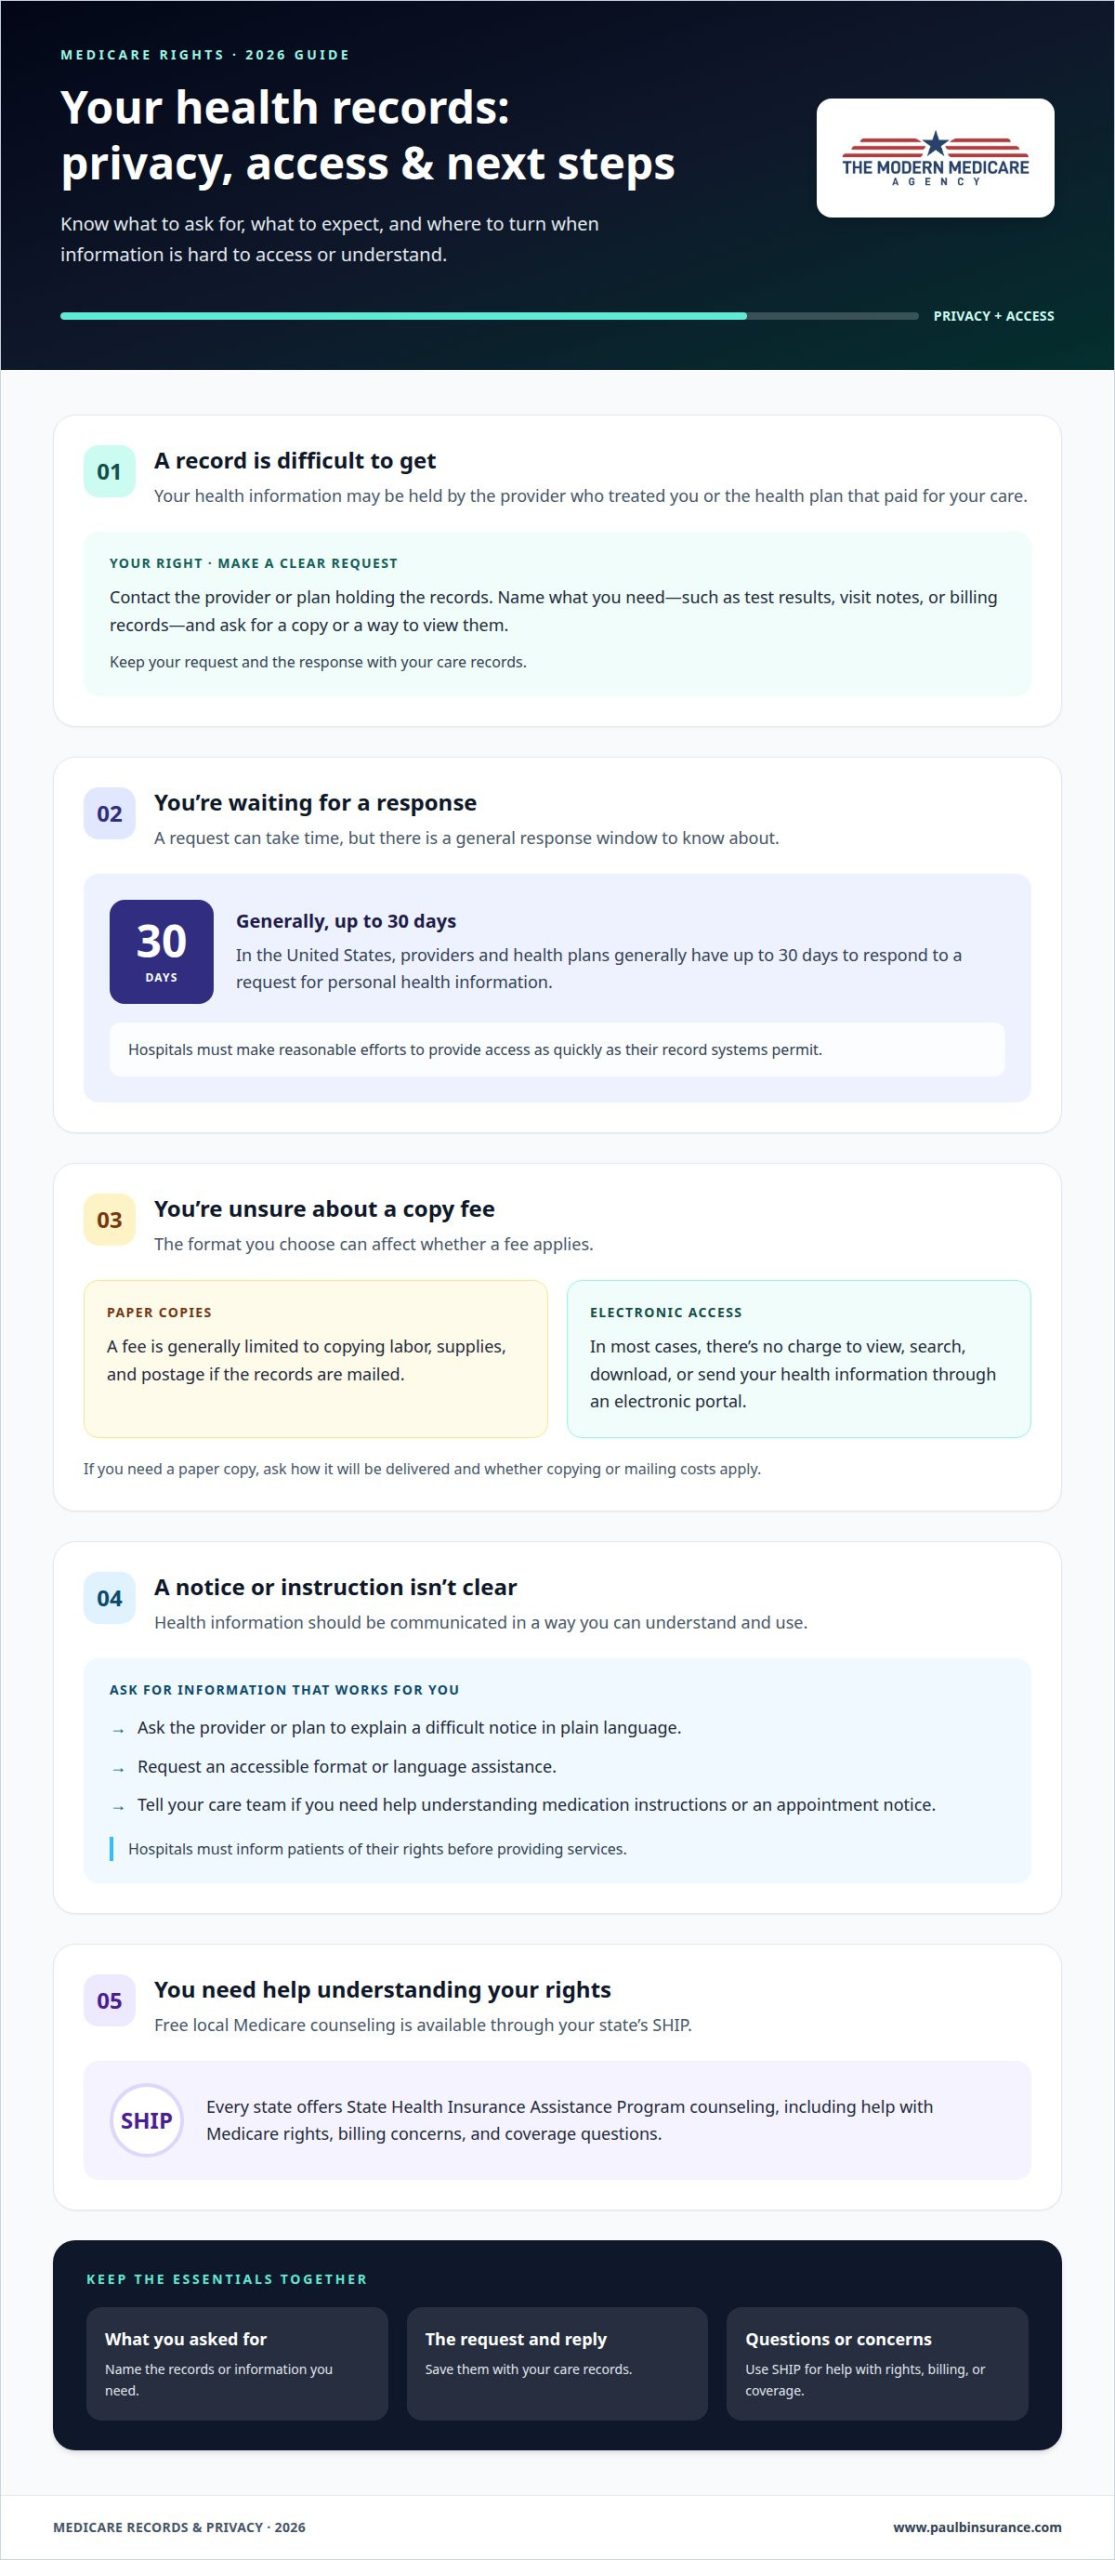
To request records, contact the provider or health plan holding them. Identify the information you need, such as test results, visit notes, or billing records. Ask for a copy or for a way to view the information. In the United States, providers and health plans generally have up to 30 days to respond to a request for personal health information, according to the U.S. Department of Health and Human Services. Hospitals must make reasonable efforts to meet legitimate access requests as quickly as their record systems permit.

A copy fee is generally limited to the cost of copying labor, supplies, and postage if the records are mailed. In most cases, you aren’t charged to view, search, download, or send your health information through an electronic portal. If you need a paper copy, ask how it will be delivered and whether copying or mailing costs apply. Keep your request and the response with your care records.

Accessible information means care details are communicated in a way you can understand and use. If a written notice is difficult to read, ask the provider or plan to explain it in plain language. You can also request an accessible format or language assistance. For example, tell the care team if you need help understanding medication instructions or an appointment notice. Hospitals must inform patients of their rights before providing services.

Access to covered health care services means Medicare rights protect access to services the law says Medicare can provide. If a Medicare drug plan denies coverage for a medicine, it must provide a written explanation of that coverage decision. Read the explanation to understand the plan’s reason and next steps. If you need help making sense of plan terms, Medicare plan information can help clarify how coverage choices relate to your needs.

Medicare beneficiaries’ privacy rights include keeping personal health information confidential and viewing or obtaining copies of medical records. Hospitals must make reasonable efforts to provide access promptly, while providers and plans generally have up to 30 days to respond to requests.

For free local counseling, contact your state’s State Health Insurance Assistance Program, or SHIP. Every state offers SHIP counseling, including help with Medicare rights, billing concerns, and coverage questions.

Medicare Advantage plan rights

Medicare Advantage members have the right to understand plan decisions and question care or coverage outcomes. The plan’s notices and instructions explain the steps that apply.

Medicare Appeals and Filing Deadlines

An appeal asks a plan to review a coverage or care decision. If your plan denies a service or payment, read the written notice for the reason and appeal instructions. Deadlines depend on the decision and notice, so follow the date stated there. Keep a copy of the notice and any records that support your request.

How do Medicare appeals work, and what are the filing deadlines? Start with the plan’s denial notice and follow its appeal process and stated deadline. If a skilled nursing facility discharge is based only on lack of improvement while you still need skilled nursing or therapy, you can appeal the discharge.

Fraud and Abuse Reporting

Reporting fraud means alerting the plan or Medicare to suspicious charges or conduct. Review any unfamiliar bill or service entry, then contact the plan using its member materials. Share the date, provider name, service description, and any related notice. Keep copies of bills and messages so the concern can be reviewed clearly.

How can beneficiaries report Medicare fraud or abuse, and what risks should they watch for? Report suspicious charges or conduct to the plan or Medicare, and keep supporting records. Treat an unexpected service entry, a bill for care you didn’t receive, or pressure to accept a service as a reason to ask for an explanation.

Ask how the plan pays doctors. Medicare Advantage plans must explain their doctor payment arrangements when members ask. This can help you understand how the plan works with its doctors. Ask the plan directly and keep its answer with your plan documents. When comparing plans, review how each handles providers and services, along with its costs and coverage terms.

Separate plan rules from Medicare coverage. Ask the plan to explain whether a benefit or service is covered. The same limit applies to Medicare representatives, SHIP counselors, and providers. If someone says a service will be covered, ask the plan to explain its decision in writing. That explanation helps you see what the plan decided and what you can do next.

Use the right review route. A coverage appeal and a care-quality complaint address different concerns. An appeal challenges a decision about coverage or payment. A quality-of-care concern focuses on the care you received. Medicare’s Beneficiary and Family Centered Care Quality Improvement Organization, or BFCC-QIO, can help with appeals, grievances, quality reviews, and medical-necessity reviews. Keep your plan notice and care records together when explaining your concern.

Before choosing or changing coverage, compare the plan’s written benefits, provider arrangements, and appeal instructions. This gives you a clearer basis for your decision and helps you know where to turn if a service is denied or a charge seems wrong.
Medicare Beneficiary Rights: Fair Treatment, Privacy and Care

Privacy and safe care

Safe care means receiving health services in a setting that protects your well-being. Under 42 C.F.R. § 482.13(c), hospital patients have the right to privacy, a safe care setting, and freedom from abuse or harassment. This applies while you receive hospital care, not just during a procedure. If a room, interaction, or care practice makes you feel unsafe, tell a staff member what happened and what concerns you.

Privacy in a hospital means staff respect your personal space and sensitive care needs. The same rule, 42 C.F.R. § 482.13(c), recognizes hospital patients’ right to privacy. For example, you can raise a concern if a conversation about your health happens where others can hear. You can also ask staff to explain how they’ll protect your privacy during an examination or treatment.

Freedom from abuse means hospital patients must be protected from abuse and harassment. Under 42 C.F.R. § 482.13(c), this protection is part of the right to a safe care setting. If someone’s words or actions make you feel threatened or mistreated, describe the event to hospital staff. Include who was involved, where it happened, and what support you need now.

Prompt notification means the hospital must notify someone you choose after admission. Under 42 C.F.R. § 482.13(b)(4), hospital patients can have a family member or representative notified promptly. Tell staff whom you want contacted and how to reach them. If you choose a representative rather than a family member, make that clear during admission so the hospital knows who should receive notice.

A care representative is someone you choose to be notified about your hospital admission. Naming that person gives you a point of contact if you need help communicating or support. For example, you might ask someone you trust to help explain a concern to staff. You still have the right to raise the concern yourself, and staff should hear your account directly.

To report a safety concern, explain the problem to hospital staff and ask for a response. Describe what happened, when it occurred, and whether you need immediate help. If the first conversation doesn’t address your concern, ask how to submit a formal grievance. Keep any written response or notes about the discussion, including the names of staff members you spoke with.

A grievance is a formal complaint about a hospital concern. Hospitals must maintain a process for resolving patient grievances promptly, including review and response time frames under 42 C.F.R. § 482.13(a)(2). Ask staff how to submit yours and how you’ll receive the response. A clear written account can help the hospital understand the event and the resolution you’re seeking.

How can Medicare beneficiaries get help understanding their coverage and rights?

In 2026, start by matching your question to the right contact. A State Health Insurance Assistance Program, or SHIP, can help you talk through Medicare questions. If you’re figuring out how to understand your rights as a Medicare beneficiary, write down what happened and what you need clarified before the conversation.

Prepare a short summary before calling. Include the date, the provider or plan involved, and the notice or bill you received. State the main issue first, then explain what response you’re seeking. Keep names, call dates, and instructions together. These notes make follow-up easier if you speak with someone else or need to revisit the decision.

Your coverage type guides where to direct benefit and cost questions. With Original Medicare, call 1-800-MEDICARE. If you’re enrolled in a Medicare health or drug plan, contact that plan first. Have your plan card or notice nearby so you can identify the service, charge, or decision clearly. Ask what steps apply and where the plan’s written instructions appear.

A Beneficiary and Family Centered Care Quality Improvement Organization, or BFCC-QIO, reviews Medicare complaints and care quality. If you’re concerned about a care decision, explain what happened in order and keep related notices nearby. The BFCC-QIO can help with appeals, grievances, quality-of-care reviews, and medical-necessity reviews. Clear dates and records help you describe the concern specifically.

The Medicare Beneficiary Ombudsman can receive unresolved Medicare-related concerns. Call 1-800-MEDICARE at 1-800-633-4227 and ask for your inquiry to be submitted to the Ombudsman. People who use a text telephone, also called TTY, can call 1-877-486-2048. Before calling, note which contacts you’ve already tried and what responses you received.

If a bill for a test, item, or service is unexpected, gather the bill and related coverage notice. Ask what the charge refers to and what decision led to it. For plan coverage questions, contact the plan first; Original Medicare benefit or cost questions go to 1-800-MEDICARE. Keep the explanation with the bill so you can refer to it if the issue remains unresolved.

For any conversation with a Medicare representative, plan employee, counselor, or provider, give complete, updated details. Ask for the next step in plain language and record the answer. If you’re still considering how to understand your rights as a Medicare beneficiary while reviewing plan choices, get support reviewing Medicare coverage options.

The Modern Medicare Agency

The Modern Medicare Agency helps eligible individuals compare Medicare coverage options and choose plans suited to their needs. If you understand your rights but feel unsure about plan choices, personalized guidance can help make the differences clearer. The agency helps compare Medicare Advantage, Medicare Supplement (Medigap), and Medicare Part D plans from over 40 carriers, with recommendations based on individual needs.

This guidance can help you assess plan options, but it doesn’t replace Medicare, your plan, or official support for complaints and appeals. For a coverage decision or unresolved concern, use the appropriate Medicare or plan process. If you’d like help reviewing Medicare plan choices, contact The Modern Medicare Agency.

Move Forward With Greater Confidence

Understanding your rights can shape how confidently you take part in future Medicare decisions. In 2026, keep your questions close when your circumstances or coverage needs change. A clear question can help you focus a conversation on what matters to you, without feeling you need to understand every detail at once.

If you’re weighing coverage options, The Modern Medicare Agency offers Medicare Advantage Plans, Medicare Supplement (Medigap) Plans, and Medicare Part D Plans. Personalized comparisons can help you assess options against your priorities. Understanding your rights as a Medicare beneficiary is an ongoing process, and support can be useful as new questions arise.

Contact The Modern Medicare Agency to discuss your Medicare coverage questions. Take the next step at your own pace, with a clearer sense of what you want to understand.

Frequently Asked Questions

What rights do Medicare beneficiaries have under federal law?

Medicare beneficiaries have rights involving care decisions, privacy, records, and complaints. For example, a hospital patient can accept or refuse treatment and participate in care planning. You can also ask to see personal health information held by providers or plans involved in your care. If a concern arises, explain what happened and ask how to raise it through the relevant hospital or plan process.

What protections do Medicare beneficiaries have against discrimination and improper billing?

Medicare rights protect beneficiaries from unethical practices, and hospital patients have protections against abuse, coercion, and retaliation. If a bill lists a test or service you don’t recognize, compare it with the care you received and ask the provider or plan to explain the charge. Keep the bill and related notices together. Clear records can help you describe the concern when seeking a review.

What rights do Medicare beneficiaries have when choosing doctors and hospitals?

People with Original Medicare can use any health care provider or specialist, or any Medicare-certified hospital that takes Medicare. Federal Medicare law also allows beneficiaries to obtain services from qualified institutions, agencies, or people who participate in Medicare. Medicare Advantage follows plan coverage rules, so whether a doctor participates in your plan matters. Before arranging non-urgent care, review the plan’s provider information and ask about coverage.

What can Medicare beneficiaries do if coverage for a service or prescription is denied?

Ask for the denial and its reason in writing, then follow the appeal instructions included with the decision. For a prescription, a Medicare drug plan must provide a written explanation of its coverage decision. Keep that notice, the prescription or service details, and related records together. If you’re unsure what to do next, contact your plan for its instructions or ask a SHIP counselor for Medicare guidance.

Paul Barrett

Article by

Paul Barrett

Paul Barrett, CMIP is the founder of The Modern Medicare Agency, an independent Medicare-only brokerage based in Melville, NY. With 18 years of Medicare-exclusive experience, a CMIP designation, and more than 5,000 clients served across 37 states, Paul is one of the most credentialed independent Medicare specialists on Long Island — and one of the most direct.

He represents 40+ carriers with no quotas and no allegiances, which means his recommendations are based entirely on what fits each client's specific situation. He is the author of Medicare Mastery Unlocked and host of the Wise Guys Retirement Talk podcast. His content is grounded in primary sources, real carrier intelligence, and 18 years of watching what happens when people get Medicare right — and when they don't.

📞 631-358-5793 | paulbinsurance.com

What Is Medicare Part B and What Does It Actually Cover?

The complete guide to Medicare’s medical insurance — every service it covers, exactly what it costs in 2026, how it works with group insurance and VA benefits, and the excess charges most people have never heard of until they get a surprise bill.

The Short Answer

Medicare Part B is medical insurance — it covers doctor visits, outpatient care, preventive services, durable medical equipment, and more. Unlike Part A, Part B is not premium-free for anyone: everyone pays a monthly premium (202.90in2026formostpeople),anannualdeductible(283), and 20% coinsurance on most covered services, with no yearly cap on that 20% under Original Medicare alone. Whether you need to enroll at 65, and whether delaying is safe, depends heavily on your employment status and your employer’s size — getting this wrong is one of the most consequential and permanent mistakes in all of Medicare.

Key Takeaways

  • Part B is never premium-free — everyone pays a monthly premium, and higher earners pay significantly more through IRMAA.
  • The 20% coinsurance under Original Medicare alone has no yearly cap — this is the single biggest financial risk in Medicare, and it’s the reason Medigap and Medicare Advantage exist.
  • Whether you can safely delay Part B without a penalty depends on your employer’s size: 20+ employees generally allows delay; fewer than 20 generally does not.
  • Missing your enrollment window triggers a permanent 10% penalty for every 12-month period you went without coverage.
  • Veterans can and generally should enroll in Part B even with VA benefits, since Medicare and VA coverage don’t coordinate — each only pays for care received within its own system.
  • “Excess charges” from non-participating providers can add up to 15% on top of what Medicare approves, and only some Medigap plans protect you from them.

What Part B Actually Covers

While Part A handles hospital room and board, Part B is the half of Original Medicare that covers medical care and most services delivered outside a hospital admission — doctor visits, outpatient procedures, and ongoing medical needs.

What’s covered

  • Doctor visits — primary care and specialists
  • Outpatient surgeries and procedures
  • Diagnostic lab work, X-rays, and MRIs
  • Emergency room visits
  • Ambulance services
  • Outpatient mental health care
  • Physical, occupational, and speech therapy
  • Chemotherapy and radiation received in an outpatient clinic
  • Durable Medical Equipment (DME) — wheelchairs, oxygen equipment, blood sugar monitors, walkers, and similar equipment
  • Ambulatory surgical center services

Preventive services: the part Medicare gets genuinely right

Most preventive services are covered at 100%, with no deductible and no copay, as long as your provider accepts Medicare assignment. This includes:

  • Your one-time “Welcome to Medicare” wellness visit, available within your first 12 months on Part B
  • Annual wellness visits after that
  • Flu shots and most other recommended vaccines
  • Mammograms
  • Colonoscopies and other cancer screenings
  • Diabetes and cardiovascular screenings
  • Many other screenings recommended by the U.S. Preventive Services Task Force

Paul’s Honest Take: This is one of the most underused parts of Medicare, full stop. I’ve had clients who paid for a private physical every year out of habit and never realized their annual wellness visit through Medicare was completely free. If you haven’t used your Welcome to Medicare visit or your annual wellness visit, that’s real value sitting on the table.

What’s NOT covered

  • Routine dental care — cleanings, fillings, dentures, extractions
  • Routine vision exams and eyeglasses
  • Hearing aids (though diagnostic hearing tests ordered by a doctor may be covered)
  • Long-term custodial nursing home care — help with daily living activities, as opposed to short-term skilled or medical care
  • Routine prescription drugs you pick up at a retail pharmacy — that’s Part D’s job, not Part B’s
  • Cosmetic surgery, unless medically necessary (such as reconstruction after an accident or mastectomy)
  • Most care received outside the United States, with very limited exceptions
  • Routine foot care, such as nail trimming, in the absence of a qualifying medical condition
  • Acupuncture, except for a narrow, specific chronic low back pain benefit
  • Concierge medicine fees and membership-style charges some practices add on top of standard care
  • Long-term care insurance-style services, including most home-based personal care that isn’t tied to a skilled medical need

Paul’s Honest Take: The dental and vision exclusions are the ones that surprise people most, especially since they’re such routine parts of healthcare for most adults. This is exactly why so many Medicare Advantage plans build dental, vision, and hearing benefits into their coverage — Original Medicare was simply never designed to include them, and that gap doesn’t go away on its own.

What Part B Costs in 2026

Part B has three separate cost components, and understanding all three matters:

Cost Component

2026 Amount

Standard monthly premium

$202.90

Annual deductible

$283

Coinsurance on most covered services

20%

The premium is deducted automatically from your Social Security check if you’re already collecting benefits. If you’re not yet collecting Social Security, you’ll receive a bill, typically every three months.

The deductible works differently than Part A’s — it’s a straightforward annual figure. You pay the first $283 of Medicare-approved outpatient costs each calendar year, and then Medicare’s cost-sharing kicks in.

The coinsurance is where the real risk lives. After your deductible is met, Medicare pays 80% of the Medicare-approved amount for most covered services, and you’re responsible for the remaining 20%. There is no yearly cap on this 20% under Original Medicare alone. If you have a $100,000 course of cancer treatment, your 20% share is $20,000 — unless you have a Medigap policy or Medicare Advantage plan absorbing that cost.

Paul’s Honest Take: I put this in bold because it’s genuinely the single most important number in this entire guide. That uncapped 20% is the whole reason Medigap and Medicare Advantage exist as products in the first place. Original Medicare by itself was never designed to protect you from a truly expensive year — it was designed to cover 80% of it and leave the rest to you.

IRMAA: What Higher Earners Actually Pay

If your income is above certain thresholds, you’ll pay more for Part B through the Income-Related Monthly Adjustment Amount (IRMAA) — based on your tax return from two years prior. For 2026, that means your 2024 income determines your premium tier.

2024 Income (Individual)

2024 Income (Married, Joint)

Total Part B / Month

$109,000 or less

$218,000 or less

$202.90

$109,001 – $137,000

$218,001 – $274,000

$284.10

$137,001 – $171,000

$274,001 – $342,000

$405.80

$171,001 – $205,000

$342,001 – $410,000

$527.50

$205,001 – $499,999

$410,001 – $749,999

$649.20

$500,000 and above

$750,000 and above

$689.90

At the top tier, you’re paying more than three times the standard premium. If your income has recently dropped — retirement, the loss of a spouse, or certain other life-changing events — you can appeal your IRMAA determination using Form SSA-44.

Do You Have to Enroll? And What Happens If You Don’t?

Technically, Part B is optional — Medicare won’t force you into it. But opting out without a valid alternative is genuinely risky, because of how the penalty structure works.

If you don’t sign up during your Initial Enrollment Period (the 7-month window around your 65th birthday) and you don’t have qualifying employer coverage, you’ll face a permanent 10% penalty added to your premium for every full 12-month period you went without Part B. That penalty doesn’t expire — you pay it for as long as you have Part B, which for most people means for the rest of your life.

Example: If you delayed enrollment by 24 full months without a valid exception, you’d pay an extra 20% on top of the standard $202.90 premium in 2026 — roughly $40.58 more, every month, permanently.

How Part B Works with Group Insurance

Just like Part A, whether you can safely delay Part B without penalty comes down to one specific number: how many employees your company has.

Companies with 20 or more employees: If you or your spouse are actively working and covered by a genuine group health plan, your workplace insurance is primary, and you can legally delay Part B without any penalty. When that employment or coverage eventually ends, you get an 8-month Special Enrollment Period to enroll in Part B penalty-free.

Companies with fewer than 20 employees: Medicare automatically becomes your primary insurer at 65, regardless of your employment status. You need to enroll in Part B right on schedule. If you don’t, your small employer’s plan can legally refuse to pay claims that Medicare should have covered first — potentially leaving you responsible for the full cost.

Paul’s Honest Take: I say this in nearly every guide I write, because it’s genuinely one of the costliest misunderstandings I encounter: “I have good coverage at work” and “I’m protected from Medicare’s enrollment deadlines” are two completely different statements, and whether the second one is true depends entirely on your employer’s size — not how generous the coverage feels. Confirm the actual employee count before you decide to delay anything.

Retiree Coverage Is Not the Same as Active Employer Coverage

This is a distinction that catches a genuinely large number of people off guard: the “20 or more employees” exception only applies to active employment. If you retire and your former employer offers you retiree health benefits — sometimes a genuinely good, comprehensive plan — that coverage does not create a Special Enrollment Period the way active group coverage does, and it does not exempt you from enrolling in Part B on time.

Paul’s Honest Take: I’ve seen this mistake more than once, and it’s an especially painful one because it happens to people who did everything right during their working years. Someone retires with a strong retiree health plan from a large employer, assumes it works the same way their active coverage did, and delays Part B — only to find out later that retiree coverage was never a valid reason to delay in the first place. The moment you stop actively working, that clock starts, regardless of how good your retiree plan looks on paper. If you’re retiring and keeping employer retiree benefits, treat enrolling in Part B as something to handle right on schedule, not something retiree coverage lets you postpone.

Why You Need Both Part A and Part B for Medigap or Medicare Advantage

Here’s a foundational requirement worth understanding clearly, since it shapes every other coverage decision in Medicare: you must be enrolled in both Part A and Part B before you can buy a Medigap policy or enroll in a Medicare Advantage plan. Neither product exists as a standalone substitute for Original Medicare — both are built specifically to work alongside it.

  • Medigap fills the cost-sharing gaps left by Original Medicare (Parts A and B) — it has nothing to fill in if you’re not enrolled in both parts to begin with.
  • Medicare Advantage legally must provide at least the same coverage as Parts A and B combined, which is only possible because you’re required to be enrolled in both before a Medicare Advantage carrier can enroll you.

Paul’s Honest Take: This surprises people who assume they can somehow “skip” Part B and go straight into a Medicare Advantage plan to avoid the extra premium. It doesn’t work that way — Part B enrollment, and its premium, is a prerequisite either way, whether you end up on Original Medicare with Medigap or on a Medicare Advantage plan. There’s no path through Medicare that avoids the Part B premium once you’re actually using the system.

Does Medicare Work If You’re a Veteran?

Yes — and if you have VA health benefits, understanding how the two systems relate is genuinely important, because they work differently than most people assume.

Medicare and VA benefits do not coordinate. These are two entirely separate systems that each pay only for care received within their own network. Medicare doesn’t pay for care you receive at a VA facility, and VA benefits don’t pay for care you receive from a non-VA doctor or hospital. You, the veteran, choose which system to use each time you seek care.

Here’s the critical point: having VA benefits does not exempt you from Medicare’s enrollment deadlines. VA coverage is not considered a qualifying reason to delay Part B without penalty. If you don’t enroll in Part B during your Initial Enrollment Period and you’re relying solely on VA benefits, you can still trigger the permanent late enrollment penalty.

Why the VA itself recommends enrolling in Medicare anyway:

  • It gives you access to civilian doctors and hospitals outside the VA system
  • VA healthcare funding depends on annual Congressional appropriations, which isn’t guaranteed to remain stable
  • If VA authorizes only part of your needed care at a non-VA facility, Medicare can help cover the rest
  • Having both gives you meaningfully more flexibility and security than relying on either system alone

Paul’s Honest Take: This is one of the most common misconceptions I run into with veterans specifically, and it’s an expensive one to get wrong. Good VA coverage feels like it should be enough, and it might genuinely handle most of your care — but it doesn’t protect you from the Part B enrollment clock the way employer coverage from a large company can. The VA itself actively encourages enrolling in Medicare Parts A and B for exactly this reason. If you have VA benefits and are approaching 65, this is worth a direct conversation before you assume you’re covered.

Veterans who enroll in Part B can also purchase a Medigap policy, which can be particularly valuable if you use non-VA providers regularly — though if you primarily rely on VA facilities for most of your care, the value of an added Medigap policy may be more limited, and worth weighing carefully.

How Long Does It Actually Take to Get Part B Approved?

This is one of the most practical, and most overlooked, pieces of planning — especially if you’re leaving a job after 65 and coordinating your Part B start date around the end of your employer coverage. Applying isn’t instant, and the timeline depends heavily on which enrollment window you’re using.

Enrollment Situation

Typical Processing Time

When Coverage Actually Starts

Initial Enrollment Period (around 65)

2–4 weeks, sometimes up to 6

1st of your birthday month (if applied in the 3 months before) or 1st of the month after you apply (if applied during or after your birthday month)

Special Enrollment Period (leaving employer coverage)

4–8 weeks, sometimes longer

1st of the month after your application is submitted

General Enrollment Period (Jan 1–Mar 31, missed window)

4–6 weeks

1st of the month after you apply

Why the Special Enrollment Period takes longer: applying after leaving employer coverage requires two forms, not one — Form CMS-40B (the actual Part B application) and Form CMS-L564 (Request for Employment Information), which your employer needs to complete to verify you had qualifying coverage. Social Security has to manually review both, which is exactly why this route consistently takes longer than a standard Initial Enrollment Period application.

Paul’s Honest Take: This timeline question comes up constantly with clients who are retiring or leaving a job after 65, and it deserves real attention — not just because of the penalty risk we’ve already covered, but because a slow approval can leave you with an actual gap in coverage if you time it too tightly. My standard advice: start this process at least 2 to 3 months before you need Part B to actually begin, not the week your employer coverage ends. If your former employer is slow to complete their portion of Form CMS-L564, that alone can hold up the entire application — so it’s worth following up with your HR or benefits department directly rather than assuming it’s been submitted.

Practical tips to avoid delays

  • Apply online through SSA.gov whenever possible. It’s consistently the fastest method — mailed or faxed forms are more prone to getting lost or delayed.
  • If you’re on a Special Enrollment Period, submit Form CMS-L564 alongside Form CMS-40B, not separately. They need to arrive together, and one incomplete form can stall the whole application.
  • Expect a short intake lag even with online applications. It can take several business days for an online submission to actually appear on a local Social Security agent’s screen — don’t panic if you call shortly after applying and they say they don’t see it yet.
  • Once approved, you don’t have to wait for your physical card. Your Medicare Beneficiary Identifier typically appears in your online Social Security or Medicare.gov account within a day or two of approval, and you can print a temporary card from there — the physical card generally arrives by mail within about 30 days.

Excess Charges: The Cost Almost Nobody Knows to Ask About

Here’s a detail that surprises even people who’ve been on Medicare for years: not every doctor who accepts Medicare agrees to accept Medicare’s approved amount as full payment.

Providers fall into three categories:

  • Participating providers accept Medicare assignment, meaning they agree to accept the Medicare-approved amount as payment in full. This covers the vast majority of providers — roughly 98% of doctors nationally.
  • Non-participating providers still accept Medicare patients but haven’t agreed to accept the standard rate. They can charge an excess charge of up to 15% above the Medicare-approved amount.
  • Opted-out providers have left the Medicare system entirely and can charge whatever they want under a private contract — Medicare pays nothing at all for care from these providers, except in emergencies.

How excess charges actually work: if the Medicare-approved amount for a service is $300 and you see a non-participating provider, they can legally charge up to an additional $45 (15%) on top, for a total bill of $345 — and that excess amount doesn’t count toward your Part B deductible.

Eight states currently prohibit or limit excess charges entirely: Connecticut, Massachusetts, Minnesota, New York, Ohio, Pennsylvania, Rhode Island, and Vermont. If you live in one of these states, you’re generally shielded from excess charges from providers within your state — though you could still face them if you receive care from a non-participating provider elsewhere.

Paul’s Honest Take: This is exactly why Medigap Plan G matters so much for people who want maximum flexibility. Plan G covers excess charges in full — Plan N does not. If you’re the kind of person who wants the freedom to see any doctor without worrying about billing surprises, that distinction is worth understanding clearly before you pick between the two. And regardless of which plan you choose, it’s always worth asking a new provider directly whether they accept Medicare assignment before your first appointment.

The HSA Rule: Part B Closes the Door Too

If you’re hoping to keep contributing to a Health Savings Account, know this clearly: enrolling in Part B — or any part of Medicare — ends your ability to make new HSA contributions. This isn’t unique to Part B; it applies the moment you enroll in Medicare in any form, including premium-free Part A.

If keeping your HSA active matters to you, the only way to legally delay both Part A and Part B is through qualifying employer coverage — which, as covered above, generally requires an employer with 20 or more employees. And because Part A enrollment can be backdated up to 6 months once you do enroll, it’s smart to stop HSA contributions 6 months before you plan to sign up for Medicare or file for Social Security, whichever comes first.

Frequently Asked Questions

Is there a cap on what I’ll pay for Part B services in a year? Not under Original Medicare alone — the 20% coinsurance has no yearly limit. A Medigap policy or Medicare Advantage plan is what actually caps your exposure.

What happens if I don’t sign up for Part B on time? You’ll generally face a permanent 10% penalty on your premium for every 12-month period you went without coverage, unless you qualify for a Special Enrollment Period through active employer coverage.

Do I need Part B if I have good coverage through a small employer? Almost certainly yes. If your employer has fewer than 20 employees, Medicare becomes your primary insurer at 65 regardless of your job coverage, and not enrolling can leave you exposed to unpaid claims and a lifelong penalty.

Do veterans need Medicare Part B if they have VA benefits? Generally, yes. Medicare and VA benefits don’t coordinate — each only pays for care within its own system — and VA coverage doesn’t exempt you from Medicare’s enrollment deadlines or penalties.

What is a Part B excess charge? An additional charge, up to 15% above the Medicare-approved amount, that a non-participating provider can legally bill you. It doesn’t count toward your deductible, and only Medigap Plan G (among current plans) covers it in full.

Can I keep contributing to my HSA if I enroll in Part B? No. Enrolling in any part of Medicare, including Part B, ends your HSA contribution eligibility going forward.

How long does it take to get approved for Part B? It depends on the enrollment window. Initial Enrollment Period applications typically process in 2–4 weeks. Special Enrollment Period applications, used when leaving employer coverage, generally take 4–8 weeks since Social Security must manually verify your prior coverage using Form CMS-L564. Start the process at least 2–3 months before you need coverage to begin, especially when coordinating around a job ending.

The Bottom Line

Part B is the half of Medicare that covers your everyday medical care — and it’s also where the real financial exposure of Original Medicare lives, thanks to that uncapped 20% coinsurance. Whether you should enroll at 65, whether you can safely delay, and how much of that exposure you’re carrying all depend on details specific to your situation: your employer’s size, your income, your VA status, and which doctors you actually see.

If you want help sorting out exactly how Part B applies to your specific circumstances — or want to understand how Medigap or Medicare Advantage could close that uncapped coinsurance gap — that’s exactly the conversation I have with clients every day, at no cost to you.

Call 631-358-5793 or visit paulbinsurance.com to set up a time to talk it through.

Paul Barrett, CMIP, is the founder of The Modern Medicare Agency, based in Melville, NY, and has spent 18+ years exclusively helping people navigate Medicare — never life insurance, never annuities, just Medicare. He’s licensed in 37 states, represents more than 40 carriers, and has personally helped over 5,000 clients choose coverage that actually fits their lives.

Figures current as of 2026 and sourced from CMS, Medicare.gov, and the Social Security Administration. Individual circumstances vary, especially around employer coverage, VA benefits, and income-based premiums — always verify your specific situation before making enrollment decisions.

Sources

Related Post

Scroll to Top

