



A Melville clinic billing staff member discusses a pending Medigap crossover claim with an older patient.

Medicare Crossover Claims: How Payment and Billing Work

What happens after Medicare processes a claim can affect the remaining medical bill. A Medicare crossover claim is a claim Medicare sends to a secondary insurer after paying or making its primary-payer decision. This lets the secondary plan review eligible costs Medicare did not cover, such as deductibles, copayments, or coinsurance.

It’s understandable to wonder whether the claim moves automatically and when the next payment will arrive. Participating secondary insurers can receive claims through Medicare’s crossover process, often within 24-48 hours after Medicare pays its portion. But not every secondary insurer participates, so some claims need to be sent separately.

This guide explains how crossover claims work, how they reach Medigap plans, what payment timing can mean for providers and patients, and why a claim may not cross over. You’ll also learn how a crossover claim differs from other Medicare secondary payer claims, so you can take the right next step if a bill or payment is delayed.

Key Takeaways

  • Understand how Medicare processes a claim first and may forward it to a participating secondary insurer for consideration of remaining costs.
  • Learn why crossover timing affects provider billing and what may happen when a claim needs to be submitted separately.
  • Recognize common crossover problems, including missing or mismatched claim details that can interrupt processing.
  • See how Medigap plans can receive eligible claims through Medicare’s crossover process and consider covered cost-sharing.
  • Distinguish a Medicare crossover from other situations where Medicare acts as the secondary payer, such as some employer coverage arrangements.

Expected crossover and payment timelines

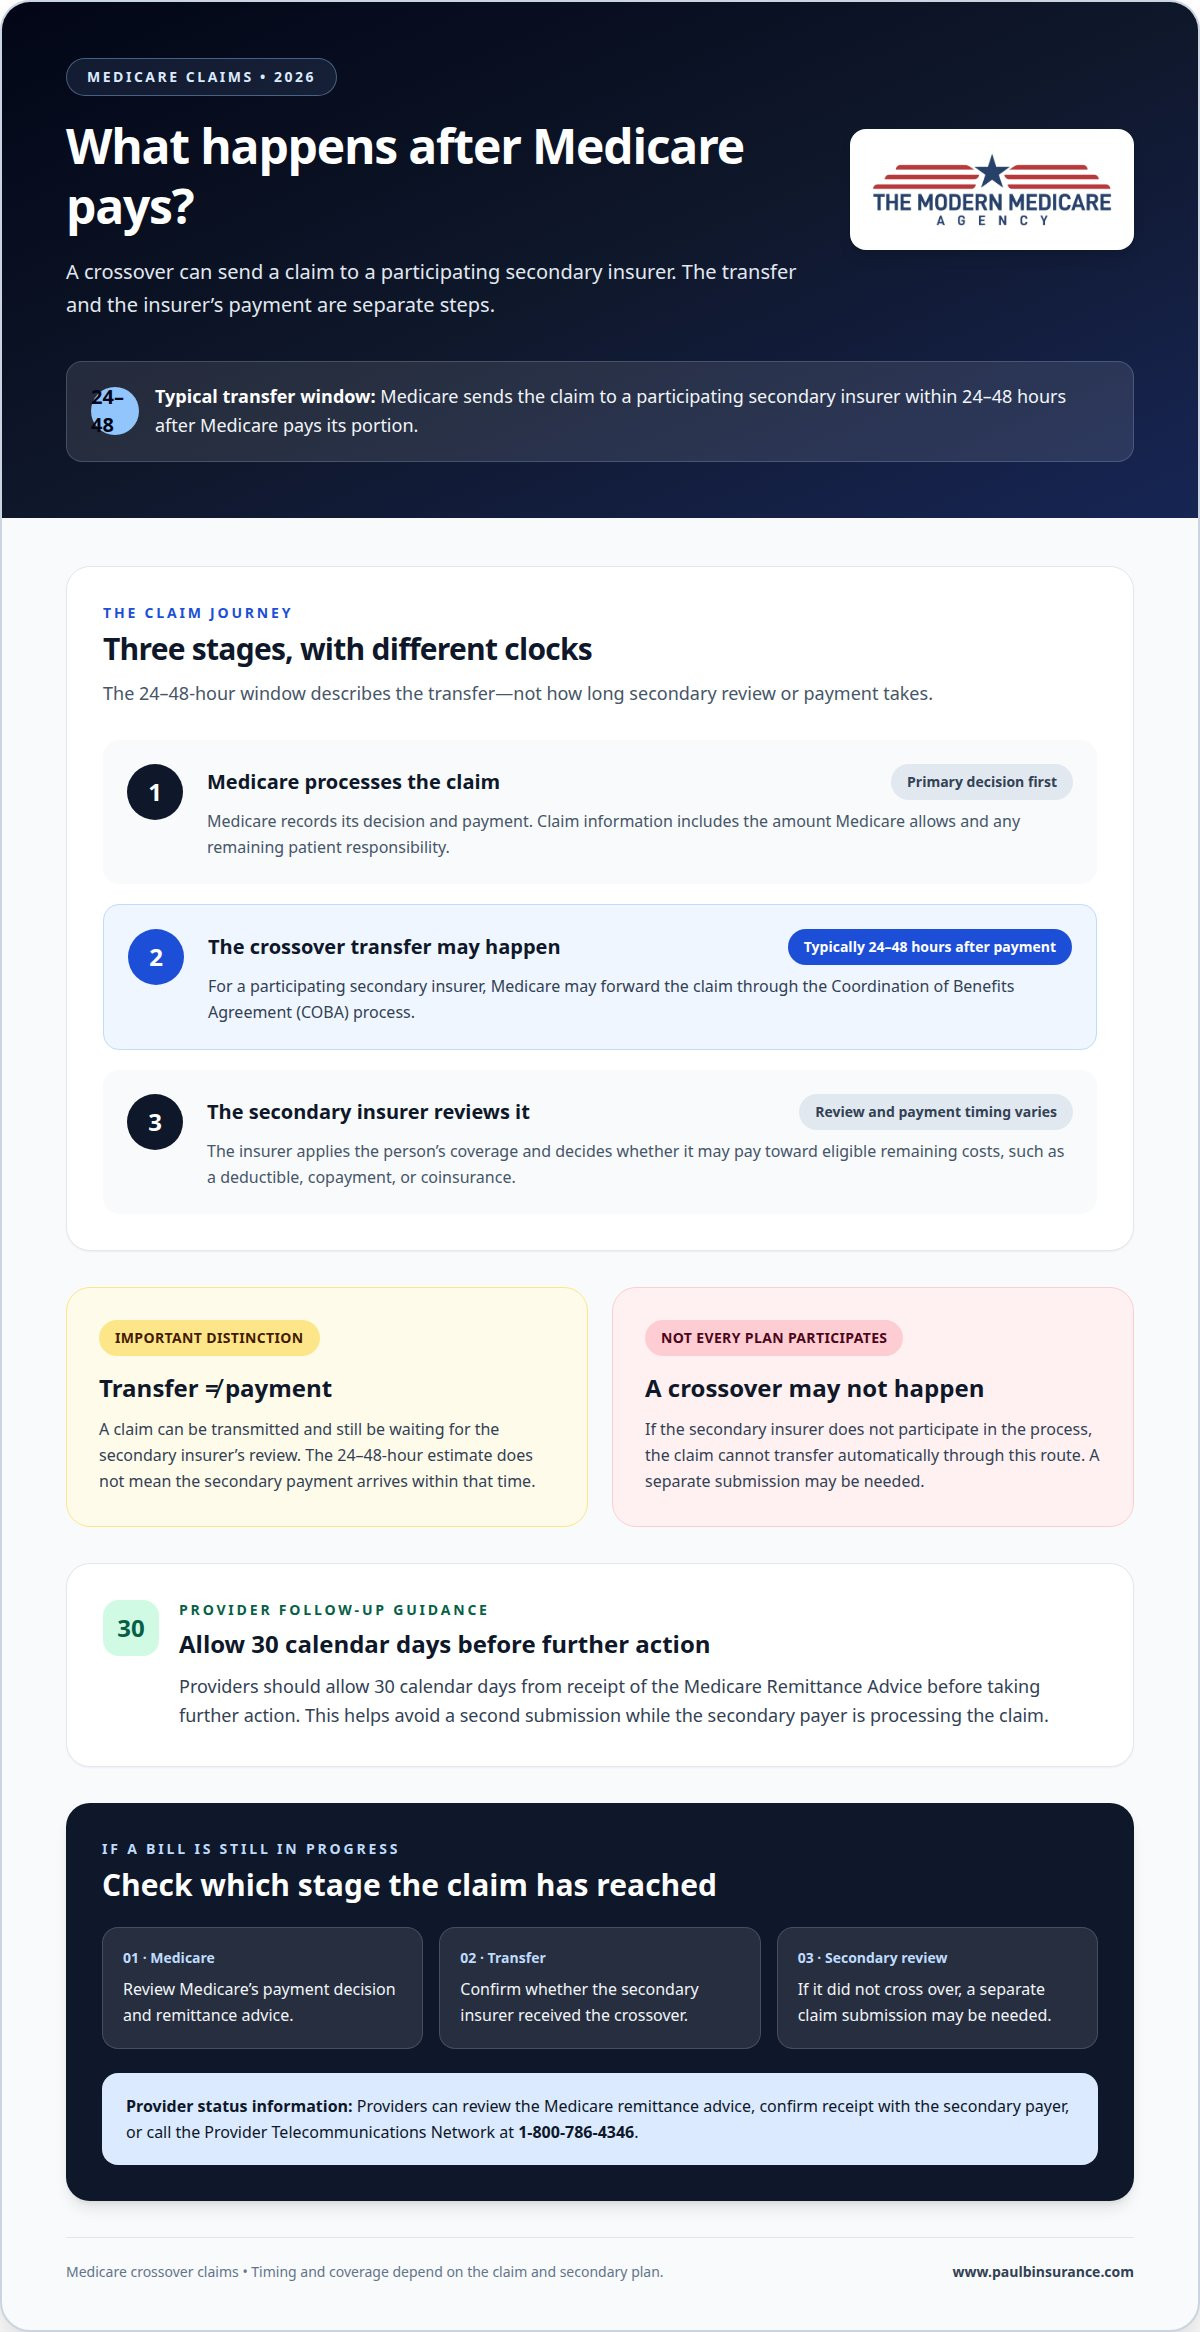
After Medicare processes a claim and pays its portion, the crossover can begin. Medicare claims are typically sent to a participating secondary insurer within 24-48 hours after Medicare pays. That window describes the transfer, not the time required for the secondary insurer to review the claim or issue payment.

The process follows a sequence. First, Medicare processes the claim as the primary payer and records its decision. Then the claim information may be sent to the secondary insurer through the Coordination of Benefits Agreement (COBA) process. The secondary insurer reviews Medicare’s decision under the person’s coverage and processes any amount it may owe.

  1. Medicare processes the claim. Its payment decision comes first when Medicare is the primary payer. The amount Medicare allows and the remaining patient responsibility are part of the claim information.
  2. The crossover transfer takes place. For participating secondary insurers, the claim is typically forwarded within 24-48 hours after Medicare’s payment.
  3. The secondary insurer reviews the claim. It applies the terms of the person’s coverage and determines whether it will pay toward remaining cost-sharing.

The Benefits Coordination & Recovery Center administers Medicare claims crossover functions on CMS’s behalf and serves as the national claims crossover contractor. Automatic crossover to a private secondary insurer may depend on whether it participates in the crossover process. Without an agreement, the claim cannot be transferred automatically through this route.

For example, when someone has Original Medicare and a participating Medigap plan, Medicare processes the claim first. If the plan receives the crossover, it can review eligible costs left after Medicare’s decision. Someone with Medicare and Medicaid may also have a crossover, but the receiving program and process can vary by state.

Keep the stages separate when tracking a bill in 2026. A claim may be processed by Medicare, transmitted to a secondary insurer, and still awaiting that insurer’s review. The 24-48-hour timeframe applies to the usual transfer after Medicare pays; it does not mean the secondary payment arrives within that same period. If the secondary plan does not receive a crossover, the claim may need another submission route. The next useful information is Medicare’s payment decision and whether the secondary insurer received the claim, because those details show which stage remains.

California payments received from a Medi-Cal recipient, except Share of Cost payments, must be refunded when the provider receives Remittance Advice Details for that service (14019.3).

In California, Medi-Cal reimbursement for a Medicare crossover claim combined with Medicare payment may not exceed Medi-Cal’s maximum allowed amount for similar services (14109.5).

Provider revenue cycle and patient billing effects

For a provider, coordination between Medicare and a secondary payer determines how a claim moves through billing. Medicare’s remittance advice records its decision and payment. The provider uses it to see what remains for the secondary plan to review, rather than treating the patient’s balance as final straight away.

How can providers check whether a Medicare claim crossed over? Review the Medicare remittance advice for information about the claim’s crossover, then confirm receipt with the secondary payer. Providers can also call the Provider Telecommunications Network at 1-800-786-4346 for crossover claim status information.

The next step depends on whether the secondary insurer participates in the COBA program. Not all secondary insurers participate, so some claims must be submitted manually. If a claim does not arrive automatically, the provider may need to send it to the secondary payer with Medicare’s remittance advice as proof of the primary decision.

Timing matters for the provider’s revenue cycle. Providers should allow 30 calendar days from receipt of the Medicare Remittance advice before taking further action. That interval helps prevent a second submission while the secondary payer is processing the claim. It also gives the provider a clear point to review whether the claim has moved forward or needs follow-up.

For patients, a crossover can reduce the need to manage separate claim paperwork, but it does not mean every remaining amount will be paid. The secondary plan applies its own coverage rules. It may consider a deductible, coinsurance, or copayment, while any amount it does not pay remains subject to the patient’s coverage and billing protections.

State Medicaid programs may have their own payment rules. In New York, Medicaid reimburses crossover claims for the deductible, coinsurance, or copayment amounts shown on the Medicare crossover claim. California sets a different limit: Medi-Cal reimbursement combined with Medicare’s payment may not exceed Medi-Cal’s maximum allowed amount for similar services.

California also has a specific protection for people eligible for both Medicare and Medi-Cal. Providers who accept these patients may not bill them for Medicare deductibles or coinsurance; those amounts may be billed only to Medi-Cal. This affects the provider’s billing steps and the patient’s responsibility, so the state program and claim details matter.

A practical billing sequence is to record Medicare’s decision, allow the stated processing period, and then confirm the secondary payer’s status. If the claim has not crossed over, a manual submission may be needed. Keeping Medicare’s remittance advice with the claim connects the primary payment to the secondary review.

Common reasons crossovers fail

If a Medicare claim doesn’t cross over, ask the provider whether the secondary plan received it. The provider may need to submit the claim manually, attaching Medicare’s remittance advice to show the primary decision.

One common cause is that the secondary insurer does not participate in the Medicare COBA crossover program. Without the required arrangement for automatic transfer, Medicare cannot route the claim through this process. The provider may need to send the claim and Medicare’s remittance advice directly to the secondary payer. The claim must still be reviewed under that plan’s rules.

Claim details can also prevent successful processing. If a member ID card includes a Coordination of Benefits Agreement ID number, providers should include it on the claim. A missing or incorrect identifier can prevent the claim from matching the person’s secondary coverage. Comparing the submitted details with the member’s card can help identify the problem.

Part B drug claims have a specific reporting requirement in Medicaid crossover billing. Each reported HCPCS code for a physician-administered drug requires a matching National Drug Code, using a 1-to-1 relationship. If a state Medicaid agency receives an associated HCPCS code without an NDC, it will likely deny the crossover claim. The provider must ensure the drug information is reported together before submission.

Eligibility can be another obstacle, even after Medicare has processed the claim. Providers must continue to verify a patient’s New York Medicaid eligibility for claims sent to Medicare. If the patient’s eligibility is not established for the claim, the state Medicaid review may not proceed as expected. Eligibility verification is a separate step that the crossover does not replace.

In Colorado, institutional inpatient claims also depend on the correct Facility Type Code. An incorrect code can disrupt processing because the claim does not identify the institutional setting as required. Providers should check this code alongside Medicare’s decision and the patient’s coverage information.

These examples show several possible failure points: participation, claim identification, required drug details, eligibility, or coding. The right correction depends on where the handoff stopped. A claim rejected for a missing NDC needs a different fix from one that never crossed over because the secondary insurer does not participate.

A clear next step for beneficiaries is to ask the provider whether Medicare’s remittance advice shows a crossover and whether the secondary payer received the claim. If it did not arrive automatically, the provider can use the remittance advice to support a manual submission. This helps distinguish a transfer problem from a secondary payer’s decision about what the coverage will pay.
Medicare Crossover Claims: How Payment and Billing Work

Crossover claims to Medigap plans

Which Medicare claims qualify for automatic crossover? Claims can be forwarded automatically when Medicare processes them as the primary payer and the secondary insurer participates in the COBA crossover process. The claim must match the insurer’s enrollee information so it can be routed for review.

COBA provides a standard arrangement for CMS and participating health insurance organizations to exchange enrollee eligibility details and Medicare-adjudicated claim information. For a Medigap plan, this coordination of benefits lets the plan receive Medicare’s decision and consider eligible Original Medicare deductibles, copayments, or coinsurance. The crossover shares the claim; it does not guarantee that the plan will pay every remaining amount.

Medigap plans typically accept professional and institutional Medicare crossover claims daily. However, a separate claim-based route under OBRA 1987 Section 4081 has a limitation: it does not support 837 institutional claims. Medigap plans using that route cannot receive institutional claims for inpatient, outpatient, home health, or hospice services through that process. The distinction matters because the type of service and the plan’s crossover arrangement affect whether automatic forwarding works.

For example, a professional claim for a doctor’s service may be sent to a participating Medigap plan after Medicare processes it. The plan then reviews the Medicare-adjudicated details against the member’s coverage. An institutional claim follows a different format, so a plan using the OBRA 1987 Section 4081 route cannot receive that claim through the same claim-based method.

How do Medicare crossover claims work for people with QMB or other Medicaid coverage? Medicare processes the claim first, then sends eligible claim information to Medicaid through the crossover process. Medicaid covers remaining Medicare cost-sharing for dual-eligible beneficiaries, subject to the applicable state program’s rules.

For someone with Qualified Medicare Beneficiary (QMB) coverage, the crossover connects Medicare’s payment decision with Medicaid’s review of remaining cost-sharing. The claim route differs from a Medigap plan’s route: Medicaid is a public program, while Medigap is private supplemental insurance. A state may also have claim-specific procedures, so the destination and processing rules depend on whether Medicaid or a Medigap plan is secondary.

In 2026, the practical question is whether the claim reached the correct secondary payer through its applicable route. A participating Medigap plan may receive eligible claims automatically, while a plan using the OBRA claim-based process has the institutional-claim limitation. If a Medicare Supplement plan is part of your coverage, understanding its role can clarify which remaining costs it may consider.

What is the difference between a Medicare crossover claim and a Medicare secondary payer claim?

A crossover claim describes how Medicare sends a processed claim to secondary coverage. A Medicare secondary payer claim describes a situation in which Medicare pays after another insurer. The difference is the direction of payment and claim movement: one term focuses on transferring information, the other on which plan pays first.

For a crossover, Medicare must be the primary payer. It processes the claim, records its decision, and then forwards claim details to an eligible secondary payer. That payer may be Medicaid, a Medigap plan, or commercial insurance. The recipient reviews the claim under its own coverage terms and considers any remaining deductible, copayment, or coinsurance.

A Medicare secondary payer situation starts differently. Another insurer is responsible for paying before Medicare. In the United States, Medicare is generally secondary to active employer coverage when the employer has at least 20 employees, according to the Centers for Medicare & Medicaid Services. The provider submits the claim to the employer plan first, then Medicare may process what remains.

Consider two examples. If someone has Original Medicare and a participating Medigap plan, Medicare pays first and may send the claim to Medigap. That is a crossover. If someone has qualifying active employer coverage and Medicare is secondary, the employer plan processes the claim before Medicare. That is a secondary payer arrangement, not the usual Medicare-first crossover sequence.

The terms can be confusing because both involve more than one payer. Keep the distinction clear by asking two questions: Which plan is primary, and is Medicare forwarding its processed claim? If Medicare pays first and forwards the claim, the crossover process may apply. If another plan must pay first, Medicare is secondary.

This distinction also explains why a claim does not always move automatically between plans. Automatic crossover depends on Medicare being primary and the receiving insurer participating in the applicable transfer process. When Medicare is secondary, the claim follows the other insurer’s payment decision first. A crossover is not simply any claim involving two insurance plans.

Understanding the payment order can help make a bill or explanation of benefits easier to interpret. Check which insurer processed the claim first, then identify whether Medicare’s decision was sent onward or followed another plan’s decision. For help understanding how supplemental coverage fits alongside Original Medicare, review Medigap coverage options.

The Modern Medicare Agency

The Modern Medicare Agency helps you understand how your Medicare coverage fits together when a claim involves more than one payer. If you’re reviewing secondary coverage or choosing a plan, its independent guidance can clarify the differences between Medicare Advantage, Medicare Supplement (Medigap), and Part D options. Understanding those differences can help you identify your coverage and ask informed questions about claim handling.

You can turn to The Modern Medicare Agency when you want personal help comparing Medicare plans and understanding how your coverage aligns with your needs. The agency offers plans from multiple carriers and provides year-round support.

For help understanding your Medicare options, contact The Modern Medicare Agency.

Make Your Next Coverage Decision With Confidence

Knowing what a Medicare crossover claim is can help you see where claim handling ends and coverage decisions begin. If a bill leaves you unsure how your current plan fits, consider whether your coverage still meets your needs and whether you understand each plan’s role. The Modern Medicare Agency offers a free Medicare consultation to help you compare options and make sense of your coverage.

The Modern Medicare Agency offers Medicare Advantage Plans, Medicare Supplement (Medigap) Plans, and Medicare Part D Plans. Its independent guidance can help you compare options based on your needs, without pressure to make a decision before you’re ready. When you’d like support with your Medicare choices, contact The Modern Medicare Agency. A clear conversation can help you take your next step with greater confidence.

Frequently Asked Questions

What is a Medicare crossover claim?

If you’re asking, “What is a Medicare crossover claim?” it’s a claim Medicare sends to another insurer after processing it. For example, when someone has Medicare and Medicaid, Medicaid may receive claim information to review remaining cost-sharing. The secondary payer makes its own decision under the person’s coverage. A crossover describes how claim information moves; it does not guarantee that the secondary plan will pay.

How does Medicare automatically send claims to Medicaid or supplemental insurance?

Medicare uses the Coordination of Benefits Agreement, or COBA, process to send eligible claim information to participating secondary payers. The transfer depends on Medicare being primary and the receiving insurer having the required arrangement. If a private insurer cannot receive claims through that process, the claim may need a separate submission. A provider can use Medicare’s remittance advice to support that submission and show the primary payer’s decision.

How long does Medicare claim crossover processing take?

Knowing what a Medicare crossover claim is also helps set timing expectations: the transfer to a participating secondary insurer typically happens within 24-48 hours after Medicare pays its portion. That timeframe covers the handoff, not the secondary plan’s full review or payment. A claim can be transmitted promptly but still need more processing before the insurer decides what it will pay. Check with the secondary payer if it remains unresolved.

What are Medicare crossover claim billing rules for providers?

Providers should bill Medicare first when it is the primary payer, then use Medicare’s remittance advice to guide any secondary claim. If an automatic crossover does not occur, the provider may submit the claim to the secondary payer with that advice. Providers should allow 30 calendar days from receiving the Medicare Remittance advice before taking further action. Accurate claim details, including required drug codes when applicable, also matter.

Can a Medicare crossover claim result in a balance bill or patient costs?

Yes, a patient may still have costs if the secondary plan does not cover every remaining amount. The plan’s coverage determines what it considers, so a crossover alone does not settle the patient’s balance. California has a specific protection: providers who accept people eligible for both Medicare and Medi-Cal may not bill them for Medicare deductibles or coinsurance; those amounts may be billed only to Medi-Cal.

Paul Barrett

Article by

Paul Barrett

Paul Barrett, CMIP is the founder of The Modern Medicare Agency, an independent Medicare-only brokerage based in Melville, NY. With 18 years of Medicare-exclusive experience, a CMIP designation, and more than 5,000 clients served across 37 states, Paul is one of the most credentialed independent Medicare specialists on Long Island — and one of the most direct.

He represents 40+ carriers with no quotas and no allegiances, which means his recommendations are based entirely on what fits each client's specific situation. He is the author of Medicare Mastery Unlocked and host of the Wise Guys Retirement Talk podcast. His content is grounded in primary sources, real carrier intelligence, and 18 years of watching what happens when people get Medicare right — and when they don't.

📞 631-358-5793 | paulbinsurance.com

What Is Medicare Part B and What Does It Actually Cover?

The complete guide to Medicare’s medical insurance — every service it covers, exactly what it costs in 2026, how it works with group insurance and VA benefits, and the excess charges most people have never heard of until they get a surprise bill.

The Short Answer

Medicare Part B is medical insurance — it covers doctor visits, outpatient care, preventive services, durable medical equipment, and more. Unlike Part A, Part B is not premium-free for anyone: everyone pays a monthly premium (202.90in2026formostpeople),anannualdeductible(283), and 20% coinsurance on most covered services, with no yearly cap on that 20% under Original Medicare alone. Whether you need to enroll at 65, and whether delaying is safe, depends heavily on your employment status and your employer’s size — getting this wrong is one of the most consequential and permanent mistakes in all of Medicare.

Key Takeaways

  • Part B is never premium-free — everyone pays a monthly premium, and higher earners pay significantly more through IRMAA.
  • The 20% coinsurance under Original Medicare alone has no yearly cap — this is the single biggest financial risk in Medicare, and it’s the reason Medigap and Medicare Advantage exist.
  • Whether you can safely delay Part B without a penalty depends on your employer’s size: 20+ employees generally allows delay; fewer than 20 generally does not.
  • Missing your enrollment window triggers a permanent 10% penalty for every 12-month period you went without coverage.
  • Veterans can and generally should enroll in Part B even with VA benefits, since Medicare and VA coverage don’t coordinate — each only pays for care received within its own system.
  • “Excess charges” from non-participating providers can add up to 15% on top of what Medicare approves, and only some Medigap plans protect you from them.

What Part B Actually Covers

While Part A handles hospital room and board, Part B is the half of Original Medicare that covers medical care and most services delivered outside a hospital admission — doctor visits, outpatient procedures, and ongoing medical needs.

What’s covered

  • Doctor visits — primary care and specialists
  • Outpatient surgeries and procedures
  • Diagnostic lab work, X-rays, and MRIs
  • Emergency room visits
  • Ambulance services
  • Outpatient mental health care
  • Physical, occupational, and speech therapy
  • Chemotherapy and radiation received in an outpatient clinic
  • Durable Medical Equipment (DME) — wheelchairs, oxygen equipment, blood sugar monitors, walkers, and similar equipment
  • Ambulatory surgical center services

Preventive services: the part Medicare gets genuinely right

Most preventive services are covered at 100%, with no deductible and no copay, as long as your provider accepts Medicare assignment. This includes:

  • Your one-time “Welcome to Medicare” wellness visit, available within your first 12 months on Part B
  • Annual wellness visits after that
  • Flu shots and most other recommended vaccines
  • Mammograms
  • Colonoscopies and other cancer screenings
  • Diabetes and cardiovascular screenings
  • Many other screenings recommended by the U.S. Preventive Services Task Force

Paul’s Honest Take: This is one of the most underused parts of Medicare, full stop. I’ve had clients who paid for a private physical every year out of habit and never realized their annual wellness visit through Medicare was completely free. If you haven’t used your Welcome to Medicare visit or your annual wellness visit, that’s real value sitting on the table.

What’s NOT covered

  • Routine dental care — cleanings, fillings, dentures, extractions
  • Routine vision exams and eyeglasses
  • Hearing aids (though diagnostic hearing tests ordered by a doctor may be covered)
  • Long-term custodial nursing home care — help with daily living activities, as opposed to short-term skilled or medical care
  • Routine prescription drugs you pick up at a retail pharmacy — that’s Part D’s job, not Part B’s
  • Cosmetic surgery, unless medically necessary (such as reconstruction after an accident or mastectomy)
  • Most care received outside the United States, with very limited exceptions
  • Routine foot care, such as nail trimming, in the absence of a qualifying medical condition
  • Acupuncture, except for a narrow, specific chronic low back pain benefit
  • Concierge medicine fees and membership-style charges some practices add on top of standard care
  • Long-term care insurance-style services, including most home-based personal care that isn’t tied to a skilled medical need

Paul’s Honest Take: The dental and vision exclusions are the ones that surprise people most, especially since they’re such routine parts of healthcare for most adults. This is exactly why so many Medicare Advantage plans build dental, vision, and hearing benefits into their coverage — Original Medicare was simply never designed to include them, and that gap doesn’t go away on its own.

What Part B Costs in 2026

Part B has three separate cost components, and understanding all three matters:

Cost Component

2026 Amount

Standard monthly premium

$202.90

Annual deductible

$283

Coinsurance on most covered services

20%

The premium is deducted automatically from your Social Security check if you’re already collecting benefits. If you’re not yet collecting Social Security, you’ll receive a bill, typically every three months.

The deductible works differently than Part A’s — it’s a straightforward annual figure. You pay the first $283 of Medicare-approved outpatient costs each calendar year, and then Medicare’s cost-sharing kicks in.

The coinsurance is where the real risk lives. After your deductible is met, Medicare pays 80% of the Medicare-approved amount for most covered services, and you’re responsible for the remaining 20%. There is no yearly cap on this 20% under Original Medicare alone. If you have a $100,000 course of cancer treatment, your 20% share is $20,000 — unless you have a Medigap policy or Medicare Advantage plan absorbing that cost.

Paul’s Honest Take: I put this in bold because it’s genuinely the single most important number in this entire guide. That uncapped 20% is the whole reason Medigap and Medicare Advantage exist as products in the first place. Original Medicare by itself was never designed to protect you from a truly expensive year — it was designed to cover 80% of it and leave the rest to you.

IRMAA: What Higher Earners Actually Pay

If your income is above certain thresholds, you’ll pay more for Part B through the Income-Related Monthly Adjustment Amount (IRMAA) — based on your tax return from two years prior. For 2026, that means your 2024 income determines your premium tier.

2024 Income (Individual)

2024 Income (Married, Joint)

Total Part B / Month

$109,000 or less

$218,000 or less

$202.90

$109,001 – $137,000

$218,001 – $274,000

$284.10

$137,001 – $171,000

$274,001 – $342,000

$405.80

$171,001 – $205,000

$342,001 – $410,000

$527.50

$205,001 – $499,999

$410,001 – $749,999

$649.20

$500,000 and above

$750,000 and above

$689.90

At the top tier, you’re paying more than three times the standard premium. If your income has recently dropped — retirement, the loss of a spouse, or certain other life-changing events — you can appeal your IRMAA determination using Form SSA-44.

Do You Have to Enroll? And What Happens If You Don’t?

Technically, Part B is optional — Medicare won’t force you into it. But opting out without a valid alternative is genuinely risky, because of how the penalty structure works.

If you don’t sign up during your Initial Enrollment Period (the 7-month window around your 65th birthday) and you don’t have qualifying employer coverage, you’ll face a permanent 10% penalty added to your premium for every full 12-month period you went without Part B. That penalty doesn’t expire — you pay it for as long as you have Part B, which for most people means for the rest of your life.

Example: If you delayed enrollment by 24 full months without a valid exception, you’d pay an extra 20% on top of the standard $202.90 premium in 2026 — roughly $40.58 more, every month, permanently.

How Part B Works with Group Insurance

Just like Part A, whether you can safely delay Part B without penalty comes down to one specific number: how many employees your company has.

Companies with 20 or more employees: If you or your spouse are actively working and covered by a genuine group health plan, your workplace insurance is primary, and you can legally delay Part B without any penalty. When that employment or coverage eventually ends, you get an 8-month Special Enrollment Period to enroll in Part B penalty-free.

Companies with fewer than 20 employees: Medicare automatically becomes your primary insurer at 65, regardless of your employment status. You need to enroll in Part B right on schedule. If you don’t, your small employer’s plan can legally refuse to pay claims that Medicare should have covered first — potentially leaving you responsible for the full cost.

Paul’s Honest Take: I say this in nearly every guide I write, because it’s genuinely one of the costliest misunderstandings I encounter: “I have good coverage at work” and “I’m protected from Medicare’s enrollment deadlines” are two completely different statements, and whether the second one is true depends entirely on your employer’s size — not how generous the coverage feels. Confirm the actual employee count before you decide to delay anything.

Retiree Coverage Is Not the Same as Active Employer Coverage

This is a distinction that catches a genuinely large number of people off guard: the “20 or more employees” exception only applies to active employment. If you retire and your former employer offers you retiree health benefits — sometimes a genuinely good, comprehensive plan — that coverage does not create a Special Enrollment Period the way active group coverage does, and it does not exempt you from enrolling in Part B on time.

Paul’s Honest Take: I’ve seen this mistake more than once, and it’s an especially painful one because it happens to people who did everything right during their working years. Someone retires with a strong retiree health plan from a large employer, assumes it works the same way their active coverage did, and delays Part B — only to find out later that retiree coverage was never a valid reason to delay in the first place. The moment you stop actively working, that clock starts, regardless of how good your retiree plan looks on paper. If you’re retiring and keeping employer retiree benefits, treat enrolling in Part B as something to handle right on schedule, not something retiree coverage lets you postpone.

Why You Need Both Part A and Part B for Medigap or Medicare Advantage

Here’s a foundational requirement worth understanding clearly, since it shapes every other coverage decision in Medicare: you must be enrolled in both Part A and Part B before you can buy a Medigap policy or enroll in a Medicare Advantage plan. Neither product exists as a standalone substitute for Original Medicare — both are built specifically to work alongside it.

  • Medigap fills the cost-sharing gaps left by Original Medicare (Parts A and B) — it has nothing to fill in if you’re not enrolled in both parts to begin with.
  • Medicare Advantage legally must provide at least the same coverage as Parts A and B combined, which is only possible because you’re required to be enrolled in both before a Medicare Advantage carrier can enroll you.

Paul’s Honest Take: This surprises people who assume they can somehow “skip” Part B and go straight into a Medicare Advantage plan to avoid the extra premium. It doesn’t work that way — Part B enrollment, and its premium, is a prerequisite either way, whether you end up on Original Medicare with Medigap or on a Medicare Advantage plan. There’s no path through Medicare that avoids the Part B premium once you’re actually using the system.

Does Medicare Work If You’re a Veteran?

Yes — and if you have VA health benefits, understanding how the two systems relate is genuinely important, because they work differently than most people assume.

Medicare and VA benefits do not coordinate. These are two entirely separate systems that each pay only for care received within their own network. Medicare doesn’t pay for care you receive at a VA facility, and VA benefits don’t pay for care you receive from a non-VA doctor or hospital. You, the veteran, choose which system to use each time you seek care.

Here’s the critical point: having VA benefits does not exempt you from Medicare’s enrollment deadlines. VA coverage is not considered a qualifying reason to delay Part B without penalty. If you don’t enroll in Part B during your Initial Enrollment Period and you’re relying solely on VA benefits, you can still trigger the permanent late enrollment penalty.

Why the VA itself recommends enrolling in Medicare anyway:

  • It gives you access to civilian doctors and hospitals outside the VA system
  • VA healthcare funding depends on annual Congressional appropriations, which isn’t guaranteed to remain stable
  • If VA authorizes only part of your needed care at a non-VA facility, Medicare can help cover the rest
  • Having both gives you meaningfully more flexibility and security than relying on either system alone

Paul’s Honest Take: This is one of the most common misconceptions I run into with veterans specifically, and it’s an expensive one to get wrong. Good VA coverage feels like it should be enough, and it might genuinely handle most of your care — but it doesn’t protect you from the Part B enrollment clock the way employer coverage from a large company can. The VA itself actively encourages enrolling in Medicare Parts A and B for exactly this reason. If you have VA benefits and are approaching 65, this is worth a direct conversation before you assume you’re covered.

Veterans who enroll in Part B can also purchase a Medigap policy, which can be particularly valuable if you use non-VA providers regularly — though if you primarily rely on VA facilities for most of your care, the value of an added Medigap policy may be more limited, and worth weighing carefully.

How Long Does It Actually Take to Get Part B Approved?

This is one of the most practical, and most overlooked, pieces of planning — especially if you’re leaving a job after 65 and coordinating your Part B start date around the end of your employer coverage. Applying isn’t instant, and the timeline depends heavily on which enrollment window you’re using.

Enrollment Situation

Typical Processing Time

When Coverage Actually Starts

Initial Enrollment Period (around 65)

2–4 weeks, sometimes up to 6

1st of your birthday month (if applied in the 3 months before) or 1st of the month after you apply (if applied during or after your birthday month)

Special Enrollment Period (leaving employer coverage)

4–8 weeks, sometimes longer

1st of the month after your application is submitted

General Enrollment Period (Jan 1–Mar 31, missed window)

4–6 weeks

1st of the month after you apply

Why the Special Enrollment Period takes longer: applying after leaving employer coverage requires two forms, not one — Form CMS-40B (the actual Part B application) and Form CMS-L564 (Request for Employment Information), which your employer needs to complete to verify you had qualifying coverage. Social Security has to manually review both, which is exactly why this route consistently takes longer than a standard Initial Enrollment Period application.

Paul’s Honest Take: This timeline question comes up constantly with clients who are retiring or leaving a job after 65, and it deserves real attention — not just because of the penalty risk we’ve already covered, but because a slow approval can leave you with an actual gap in coverage if you time it too tightly. My standard advice: start this process at least 2 to 3 months before you need Part B to actually begin, not the week your employer coverage ends. If your former employer is slow to complete their portion of Form CMS-L564, that alone can hold up the entire application — so it’s worth following up with your HR or benefits department directly rather than assuming it’s been submitted.

Practical tips to avoid delays

  • Apply online through SSA.gov whenever possible. It’s consistently the fastest method — mailed or faxed forms are more prone to getting lost or delayed.
  • If you’re on a Special Enrollment Period, submit Form CMS-L564 alongside Form CMS-40B, not separately. They need to arrive together, and one incomplete form can stall the whole application.
  • Expect a short intake lag even with online applications. It can take several business days for an online submission to actually appear on a local Social Security agent’s screen — don’t panic if you call shortly after applying and they say they don’t see it yet.
  • Once approved, you don’t have to wait for your physical card. Your Medicare Beneficiary Identifier typically appears in your online Social Security or Medicare.gov account within a day or two of approval, and you can print a temporary card from there — the physical card generally arrives by mail within about 30 days.

Excess Charges: The Cost Almost Nobody Knows to Ask About

Here’s a detail that surprises even people who’ve been on Medicare for years: not every doctor who accepts Medicare agrees to accept Medicare’s approved amount as full payment.

Providers fall into three categories:

  • Participating providers accept Medicare assignment, meaning they agree to accept the Medicare-approved amount as payment in full. This covers the vast majority of providers — roughly 98% of doctors nationally.
  • Non-participating providers still accept Medicare patients but haven’t agreed to accept the standard rate. They can charge an excess charge of up to 15% above the Medicare-approved amount.
  • Opted-out providers have left the Medicare system entirely and can charge whatever they want under a private contract — Medicare pays nothing at all for care from these providers, except in emergencies.

How excess charges actually work: if the Medicare-approved amount for a service is $300 and you see a non-participating provider, they can legally charge up to an additional $45 (15%) on top, for a total bill of $345 — and that excess amount doesn’t count toward your Part B deductible.

Eight states currently prohibit or limit excess charges entirely: Connecticut, Massachusetts, Minnesota, New York, Ohio, Pennsylvania, Rhode Island, and Vermont. If you live in one of these states, you’re generally shielded from excess charges from providers within your state — though you could still face them if you receive care from a non-participating provider elsewhere.

Paul’s Honest Take: This is exactly why Medigap Plan G matters so much for people who want maximum flexibility. Plan G covers excess charges in full — Plan N does not. If you’re the kind of person who wants the freedom to see any doctor without worrying about billing surprises, that distinction is worth understanding clearly before you pick between the two. And regardless of which plan you choose, it’s always worth asking a new provider directly whether they accept Medicare assignment before your first appointment.

The HSA Rule: Part B Closes the Door Too

If you’re hoping to keep contributing to a Health Savings Account, know this clearly: enrolling in Part B — or any part of Medicare — ends your ability to make new HSA contributions. This isn’t unique to Part B; it applies the moment you enroll in Medicare in any form, including premium-free Part A.

If keeping your HSA active matters to you, the only way to legally delay both Part A and Part B is through qualifying employer coverage — which, as covered above, generally requires an employer with 20 or more employees. And because Part A enrollment can be backdated up to 6 months once you do enroll, it’s smart to stop HSA contributions 6 months before you plan to sign up for Medicare or file for Social Security, whichever comes first.

Frequently Asked Questions

Is there a cap on what I’ll pay for Part B services in a year? Not under Original Medicare alone — the 20% coinsurance has no yearly limit. A Medigap policy or Medicare Advantage plan is what actually caps your exposure.

What happens if I don’t sign up for Part B on time? You’ll generally face a permanent 10% penalty on your premium for every 12-month period you went without coverage, unless you qualify for a Special Enrollment Period through active employer coverage.

Do I need Part B if I have good coverage through a small employer? Almost certainly yes. If your employer has fewer than 20 employees, Medicare becomes your primary insurer at 65 regardless of your job coverage, and not enrolling can leave you exposed to unpaid claims and a lifelong penalty.

Do veterans need Medicare Part B if they have VA benefits? Generally, yes. Medicare and VA benefits don’t coordinate — each only pays for care within its own system — and VA coverage doesn’t exempt you from Medicare’s enrollment deadlines or penalties.

What is a Part B excess charge? An additional charge, up to 15% above the Medicare-approved amount, that a non-participating provider can legally bill you. It doesn’t count toward your deductible, and only Medigap Plan G (among current plans) covers it in full.

Can I keep contributing to my HSA if I enroll in Part B? No. Enrolling in any part of Medicare, including Part B, ends your HSA contribution eligibility going forward.

How long does it take to get approved for Part B? It depends on the enrollment window. Initial Enrollment Period applications typically process in 2–4 weeks. Special Enrollment Period applications, used when leaving employer coverage, generally take 4–8 weeks since Social Security must manually verify your prior coverage using Form CMS-L564. Start the process at least 2–3 months before you need coverage to begin, especially when coordinating around a job ending.

The Bottom Line

Part B is the half of Medicare that covers your everyday medical care — and it’s also where the real financial exposure of Original Medicare lives, thanks to that uncapped 20% coinsurance. Whether you should enroll at 65, whether you can safely delay, and how much of that exposure you’re carrying all depend on details specific to your situation: your employer’s size, your income, your VA status, and which doctors you actually see.

If you want help sorting out exactly how Part B applies to your specific circumstances — or want to understand how Medigap or Medicare Advantage could close that uncapped coinsurance gap — that’s exactly the conversation I have with clients every day, at no cost to you.

Call 631-358-5793 or visit paulbinsurance.com to set up a time to talk it through.

Paul Barrett, CMIP, is the founder of The Modern Medicare Agency, based in Melville, NY, and has spent 18+ years exclusively helping people navigate Medicare — never life insurance, never annuities, just Medicare. He’s licensed in 37 states, represents more than 40 carriers, and has personally helped over 5,000 clients choose coverage that actually fits their lives.

Figures current as of 2026 and sourced from CMS, Medicare.gov, and the Social Security Administration. Individual circumstances vary, especially around employer coverage, VA benefits, and income-based premiums — always verify your specific situation before making enrollment decisions.

Sources

Related Post

Scroll to Top

