



What Is a Medicare-Approved Amount? A Clear Guide for 2026

What Is a Medicare-Approved Amount? A Clear Guide for 2026

Could the number Medicare approves be different from the amount you owe? Yes. If you’re asking what is a medicare-approved amount, think of it as Medicare’s payment benchmark for a covered service, not automatically your final bill. The difference between that amount and a provider’s charge can feel confusing, especially when you’re planning for care.

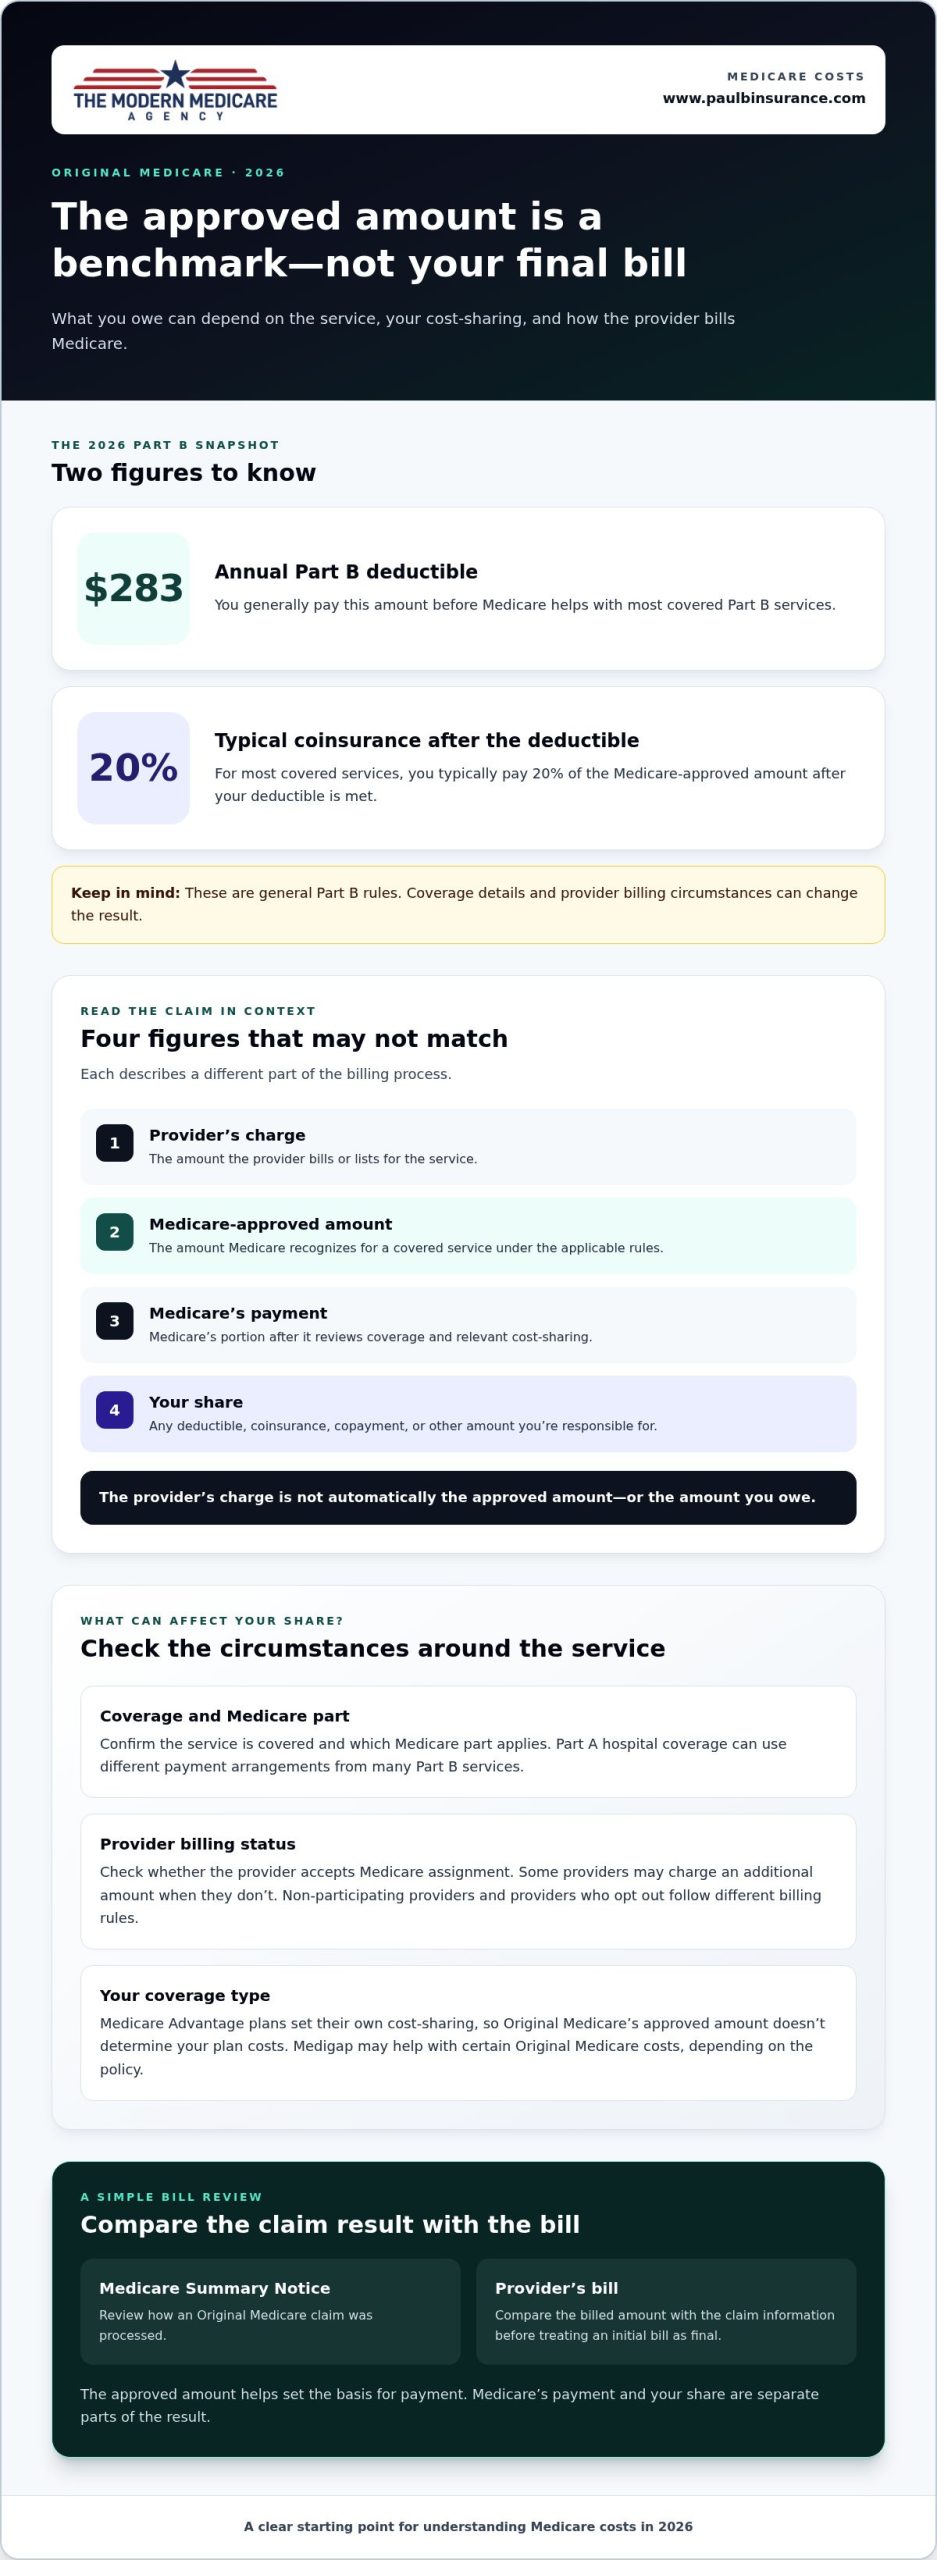
Your share depends on more than the approved amount. With Original Medicare Part B in 2026, you generally pay the $283 annual deductible before Medicare helps with most covered services. After that, you typically pay 20% of the approved amount. A provider’s billing status can also matter: some providers may charge an additional amount when they don’t accept Medicare assignment.

This guide explains the term in plain language and shows how provider charges, deductibles, and coinsurance can affect what you owe. You’ll also learn what to review before care and how Medigap or Medicare Advantage can change the way costs are handled. With a few clear details, you can approach a service or bill with more confidence.

Key Takeaways

  • Knowing what is a medicare-approved amount can help you distinguish Medicare’s payment benchmark from a provider’s charge and your final share.
  • Before care, check whether the service is covered and whether the provider accepts Medicare assignment.
  • Compare your Medicare Summary Notice with the provider’s bill to review how an Original Medicare claim was processed.
  • Medicare Advantage plans set their own cost-sharing, while Medigap may help with certain Original Medicare costs, depending on the policy.
  • Provider billing status matters: non-participating providers and providers who opt out follow different billing rules.

What Is the Medicare-Approved Amount? Start With the Meaning

The Medicare-approved amount is the payment amount Original Medicare recognizes for a covered service or medical item under the rules that apply to it. If you’re asking what is a medicare-approved amount, the key point is that it’s a benchmark for payment, not automatically the amount you owe. How Medicare uses that benchmark can vary by service and the rules that apply.

Four figures can appear in the billing process, and they don’t necessarily match:

  • Provider’s charge: The amount the provider bills or lists for the service.
  • Medicare-approved amount: The amount Medicare recognizes for the covered service under applicable rules.
  • Medicare’s payment: The portion Medicare pays after considering coverage and relevant cost-sharing.
  • Your share: Any deductible, coinsurance, copayment, or other amount you’re responsible for under the circumstances.

Knowing how these terms fit together can make a bill easier to read. For broader background on how Medicare’s parts and coverage work, see the Medicare (United States) Wikipedia page. The details below focus on Original Medicare. Plan-specific costs follow different rules.

How the approved amount differs from the provider’s charge

A provider’s listed charge and the Medicare-approved amount may be different. That difference doesn’t tell you your final responsibility on its own. The result depends on the service, coverage, and billing circumstances, including the provider’s relationship with Medicare.

Hypothetical example: Imagine a provider lists a charge for a covered service, but Medicare recognizes a different approved amount for it. Medicare then processes the claim under the rules for that service. The provider’s listed charge isn’t automatically the amount Medicare uses, and neither figure alone tells you precisely what you’ll owe.

What the phrase means for your share

Your share depends on how Medicare applies coverage and cost-sharing to the claim. These terms describe different ways costs may be divided:

  • Deductible: An amount you may need to pay before Medicare begins paying its share for certain services.
  • Coinsurance: A percentage of an applicable cost that you may owe.
  • Copayment: A set amount you may owe for a covered service.

For example, under Original Medicare Part B in 2026, the annual deductible is $283. After it’s met, you typically pay 20% of the Medicare-approved amount for most covered services. That’s a general rule, not a promise that Medicare pays the full remaining amount for every service. Coverage details and provider billing circumstances can affect the result.

Treat the approved amount as one part of the calculation, not a prediction of your bill. To understand what you may owe, consider it alongside Medicare’s payment, your applicable cost-sharing, and how the service was billed.

How the Medicare-Approved Amount Relates to Medicare Payment

The approved amount is one step in the payment process, not the whole calculation. Under Original Medicare, the general sequence is: a service is covered, Medicare applies the payment rules for that service, and the claim is used to determine Medicare’s payment and any cost-sharing you may owe. If you’re asking what is a medicare-approved amount, remember that it helps set the basis for payment, but doesn’t reveal the final division of costs by itself.

What happens after a covered service is billed

After care, the provider submits a claim for processing. Medicare reviews whether the service is covered and applies the rules for that service and your coverage. The approved amount helps determine payment, but Medicare’s share and your share are separate parts of the result. Your responsibility may depend on cost-sharing and billing circumstances, so the provider’s initial charge may not show the final amount.

For example, a claim for a covered outpatient service may be processed under Part B rules. Medicare determines its share, then applies any deductible or coinsurance that affects your responsibility. Another service may follow different rules. Claim processing can take time, so wait for the claim information before treating an initial bill as the final result.

Why the Medicare part and coverage type matter

The approved-amount concept is especially useful for understanding many Original Medicare Part B services, including doctor and outpatient care. But it isn’t a universal formula for every Medicare payment. Part A hospital coverage can use different payment arrangements, so an inpatient stay shouldn’t be read as a single office-service claim.

Coverage type matters, too. Original Medicare has its own payment and cost-sharing rules. Medicare Advantage plans use plan-specific arrangements, so don’t assume an Original Medicare approved amount determines what you pay under a Medicare Advantage plan. Check the rules for the coverage you have and the service you received.

For a clearer picture, identify the Medicare part involved, confirm whether the service is covered, and review how the claim was processed. Medicare’s official explanation of Medicare costs describes how approved amounts relate to costs such as deductibles and coinsurance. Look for guidance specific to your service and coverage, since a general explanation may not answer every billing question.

If you’re reviewing coverage choices rather than a specific bill, a free Medicare review with an independent Medicare broker can help you discuss how Medicare Advantage, Medigap, or Part D coverage may relate to your needs. For an individual claim, use Medicare’s processed claim information as your reference point.

Accepting Assignment vs. Other Provider Billing: What Changes?

A provider’s relationship with Medicare can affect how a covered service is billed. The key question isn’t only whether the office “takes Medicare,” but whether it accepts Medicare assignment for the service. Provider status can shape your billing, but it doesn’t determine your final bill by itself. Your coverage, the service, and any applicable cost-sharing still matter.

Provider status What it generally means What to keep in mind
Accepts assignment Agrees to accept the Medicare-approved amount as full payment for covered services. You may still owe applicable cost-sharing, such as a deductible or coinsurance.
Non-participating Accepts Medicare but may not accept assignment for every service. Billing rules can vary by service. Check current Medicare guidance for possible additional charges.
Opted out Has a different arrangement with Medicare, often involving a private contract. Medicare generally doesn’t pay for services covered by that arrangement. Confirm the rules for your situation.

What accepting assignment means

When a provider accepts assignment, they agree to accept Medicare’s approved amount as full payment for a covered service. “Full payment” doesn’t mean the service is automatically free to you. You may still owe your deductible or coinsurance, depending on the service and your coverage. Assignment explains the provider’s billing agreement, but doesn’t guarantee a particular claim result or out-of-pocket amount.

What to understand about non-participating and opt-out providers

A non-participating provider accepts Medicare but may decide whether to accept assignment for a particular service. An opt-out provider has a different arrangement, and Medicare generally doesn’t pay for services provided under a private contract. These statuses aren’t interchangeable. The billing rules and your responsibility depend on the circumstances, so use current Medicare.gov guidance for the service involved.

Before care, use Medicare’s current guidance to understand whether assignment applies to the service. A general statement that an office takes Medicare may not explain whether it accepts assignment for that specific service. If assignment doesn’t apply, review the relevant billing rules and your coverage documents to understand what may affect your responsibility.

For example, two offices may both see Original Medicare patients yet handle assignment differently. One may accept the approved amount as full payment for a covered service, subject to your cost-sharing. Another may not accept assignment for that service, so different billing rules could apply. Don’t assume the same answer applies to every service from the same provider.

In 2026, verify provider status and applicable billing limits using Medicare’s current provider guidance, especially if you’re concerned about additional charges. If you receive a bill that doesn’t seem to match what you expected, compare it with the processed claim information before assuming the provider’s listed charge is the amount you owe. Understanding whether assignment applies gives you a clearer starting point, while the processed claim and your coverage help clarify your actual responsibility.
What Is a Medicare-Approved Amount? A Clear Guide for 2026

How to Check the Approved Amount and Review a Medicare Bill

A bill is easier to understand when you review it alongside the claim decision and your coverage. A pre-service estimate can help you prepare, but it isn’t the same as the final amount after Original Medicare processes a claim. Use this step-by-step approach to organize the details and spot questions worth resolving.

  1. Identify the service. Note the date of care, the service or item received, and the provider’s name. Keep any appointment paperwork or estimate with your records.
  2. Check coverage. Confirm which Medicare coverage applies and whether the service is covered under the rules for your situation. The term “what is a medicare-approved amount” is most useful when you know which service and Medicare part the claim relates to.
  3. Review provider status. Before care, use Medicare’s guidance to understand whether the provider accepts assignment for the specific service. Keep in mind that an estimate may not reflect the final claim decision.
  4. Compare the documents. After Original Medicare processes the claim, compare the Medicare Summary Notice (MSN) with the provider’s bill. Review the service description, Medicare’s payment, and any amount shown as your responsibility.

Questions to consider before a service

Keep the details specific: the service name, date, provider, and whether Medicare assignment applies. Record any information you receive before care so you can compare it with the claim documents later. An estimate may be useful for planning, but don’t assume it gives the exact final amount.

What to compare after Medicare processes a claim

The MSN summarizes processed Original Medicare claims and can help you see how Medicare handled a service. Match its service description and claim details to the provider’s bill, then check how the notice explains Medicare’s payment and any remaining responsibility. If a figure or service description doesn’t make sense, use the contact information on the notice or Medicare.gov to get clarification about the claim.

If the documents don’t match, pause before assuming either figure is the final answer. Check that you’re comparing the same service and date, and note whether the bill arrived before or after the claim was processed. A pre-service estimate, the provider’s bill, and the MSN serve different purposes. If you still can’t reconcile them, follow the instructions on the MSN or use Medicare’s official information to understand the specific line item and how it was handled.

If reviewing a claim leads you to broader questions about how your coverage fits your needs, a free Medicare review can help you discuss coverage choices. For a specific bill, rely on the processed claim and official billing information.

How the Approved Amount Fits With Medicare Advantage and Medigap

The approved amount is most directly useful when you’re looking at Original Medicare billing. Your coverage type matters, though. In 2026, don’t assume that an amount used to process an Original Medicare claim automatically tells you what you’ll pay under another kind of coverage. Medicare Advantage and Medigap relate to costs in different ways, and each plan’s terms matter.

How Medicare Advantage changes the cost-sharing context

Medicare Advantage plans provide an alternative way to receive Medicare coverage. For covered services, the plan’s terms determine your cost-sharing. That means the Original Medicare approach to an approved amount shouldn’t be applied automatically to a Medicare Advantage bill. Check the plan documents for the service and how your share is calculated. If you’re learning how this coverage works, these Medicare Advantage plan basics can help explain the plan-specific context.

For example, if you receive care while enrolled in a Medicare Advantage plan, the plan’s explanation of your responsibility is the relevant starting point. The approved amount may not explain the whole calculation in the same way it does for Original Medicare. Review the plan information and claim details together, and avoid assuming that provider billing rules for Original Medicare apply unchanged.

Where Medigap may fit with Original Medicare costs

Medigap, also called Medicare Supplement insurance, works alongside Original Medicare and may help pay certain costs left to you under Original Medicare. What it helps cover depends on the specific policy. Don’t assume every Medigap policy pays the same costs or covers every amount shown on a bill. Review the policy terms and the processed Original Medicare claim together. These Medicare Supplement insurance basics explain how Medigap fits with Original Medicare.

This distinction can help answer a common question: what is a medicare-approved amount if you have other coverage? It remains part of understanding an Original Medicare claim, but it doesn’t replace the terms of a Medicare Advantage plan or tell you by itself what a Medigap policy will pay. Your coverage documents are essential to interpreting your share.

When reviewing costs, first identify whether the service was billed through Original Medicare or a Medicare Advantage plan. Then use the relevant plan or policy information to understand any remaining responsibility. If you’re weighing coverage choices rather than trying to resolve a specific bill, a free Medicare review with an independent Medicare broker can provide educational guidance. It isn’t a substitute for official claim or billing information, but it can help you discuss how Medicare Advantage or Medigap may fit your needs.

Take Your Next Coverage Step With Confidence

Understanding what is a medicare-approved amount can make a confusing bill feel more manageable. Keep claim questions grounded in official billing information, and use coverage questions to decide what you’d like to learn about your options. You don’t have to make every decision at once. Start with the question that matters most to you.

Paul B Insurance, operating as The Modern Medicare Agency, is an independent Medicare broker. The agency compares Medicare Advantage, Medigap, and Part D options from 40+ carriers. It brings 18 years of experience and 5,000+ clients served. Its service states are NY, CA, FL, TX, NC, +32 more states. A free initial consultation and Medicare review can help you talk through how coverage choices relate to your needs. This guidance is for coverage questions, not a substitute for official claim or billing information.

Schedule your free Medicare review when you’re ready to explore your options. Take it one question at a time and move forward with greater confidence.

Frequently Asked Questions

Is the Medicare-approved amount the same as the amount I owe?

No. The Medicare-approved amount is a payment benchmark for a covered service, not a statement of your personal bill. Your responsibility depends on Medicare’s payment, any deductible or coinsurance that applies, and provider billing rules. If you’re trying to understand what is a medicare-approved amount on a claim, compare the processed claim information with the provider’s bill. The approved amount alone can’t tell you the final amount you owe.

Can a Medicare-approved amount apply to a service Medicare does not cover?

The term concerns services Medicare covers under the rules that apply to your situation. If a service isn’t covered, don’t assume Medicare will pay a share based on an approved amount. If you’re unsure about a service recommended during an appointment, check coverage guidance for that specific service and review any claim decision. Coverage can depend on the details, so avoid drawing conclusions from a provider’s estimate alone.

How much of the Medicare-approved amount does Medicare pay?

There isn’t one payment amount that applies to every service or person. Medicare’s share depends on the coverage involved and the cost-sharing rules that apply, including any deductible or coinsurance. For a specific claim, look at the processed claim information to see how Medicare handled it and what responsibility remains. Medicare’s current guidance for your coverage and service can help clarify details that a general explanation can’t answer.

What happens if Medicare denies a claim?

A denial may mean Medicare didn’t approve payment for the service as it was billed, so the approved-amount concept alone may not explain what you owe. Start by reading the Medicare Summary Notice (MSN) for the stated reason and any instructions. The reason matters, and next steps can depend on the decision. If the notice is unclear, follow its guidance and use current Medicare information to understand your options.

Does the Medicare-approved amount apply to Part D prescription drugs?

This term is generally used to explain Medicare payment for covered health services. It isn’t a simple way to describe the price of a Part D prescription drug. Your prescription costs depend on your Part D plan and the medication involved. For a specific drug, check your plan’s current drug information, including the details for that medication. This gives you a more relevant picture than applying a medical-service payment term to a prescription.

Is the Medicare-approved amount the same under Medicare Advantage?

Don’t assume so. Medicare Advantage plans have their own terms for member cost-sharing, so Original Medicare provider-billing explanations may not determine what you owe. For a covered service, check your plan documents and the claim information issued through the plan. If an office bill and plan claim details appear different, use the plan’s explanation of the claim to identify what was processed and what amount is listed as your responsibility.

What should I do if my provider’s bill does not match my Medicare Summary Notice?

Compare the service description, claim status, and patient-responsibility information on both documents. Check that they refer to the same date and service, since a bill may not reflect the claim’s processed status. If the difference remains unclear, use the contact details on official Medicare documents or Medicare.gov to clarify the claim. Ask about the specific line or figure, and keep the notice and bill nearby so you can refer to the same information.

Paul Barrett

Article by

Paul Barrett

Paul Barrett, CMIP is the founder of The Modern Medicare Agency, an independent Medicare-only brokerage based in Melville, NY. With 18 years of Medicare-exclusive experience, a CMIP designation, and more than 5,000 clients served across 37 states, Paul is one of the most credentialed independent Medicare specialists on Long Island — and one of the most direct.

He represents 40+ carriers with no quotas and no allegiances, which means his recommendations are based entirely on what fits each client's specific situation. He is the author of Medicare Mastery Unlocked and host of the Wise Guys Retirement Talk podcast. His content is grounded in primary sources, real carrier intelligence, and 18 years of watching what happens when people get Medicare right — and when they don't.

📞 631-358-5793 | paulbinsurance.com

What Is Medicare Part B and What Does It Actually Cover?

The complete guide to Medicare’s medical insurance — every service it covers, exactly what it costs in 2026, how it works with group insurance and VA benefits, and the excess charges most people have never heard of until they get a surprise bill.

The Short Answer

Medicare Part B is medical insurance — it covers doctor visits, outpatient care, preventive services, durable medical equipment, and more. Unlike Part A, Part B is not premium-free for anyone: everyone pays a monthly premium (202.90in2026formostpeople),anannualdeductible(283), and 20% coinsurance on most covered services, with no yearly cap on that 20% under Original Medicare alone. Whether you need to enroll at 65, and whether delaying is safe, depends heavily on your employment status and your employer’s size — getting this wrong is one of the most consequential and permanent mistakes in all of Medicare.

Key Takeaways

  • Part B is never premium-free — everyone pays a monthly premium, and higher earners pay significantly more through IRMAA.
  • The 20% coinsurance under Original Medicare alone has no yearly cap — this is the single biggest financial risk in Medicare, and it’s the reason Medigap and Medicare Advantage exist.
  • Whether you can safely delay Part B without a penalty depends on your employer’s size: 20+ employees generally allows delay; fewer than 20 generally does not.
  • Missing your enrollment window triggers a permanent 10% penalty for every 12-month period you went without coverage.
  • Veterans can and generally should enroll in Part B even with VA benefits, since Medicare and VA coverage don’t coordinate — each only pays for care received within its own system.
  • “Excess charges” from non-participating providers can add up to 15% on top of what Medicare approves, and only some Medigap plans protect you from them.

What Part B Actually Covers

While Part A handles hospital room and board, Part B is the half of Original Medicare that covers medical care and most services delivered outside a hospital admission — doctor visits, outpatient procedures, and ongoing medical needs.

What’s covered

  • Doctor visits — primary care and specialists
  • Outpatient surgeries and procedures
  • Diagnostic lab work, X-rays, and MRIs
  • Emergency room visits
  • Ambulance services
  • Outpatient mental health care
  • Physical, occupational, and speech therapy
  • Chemotherapy and radiation received in an outpatient clinic
  • Durable Medical Equipment (DME) — wheelchairs, oxygen equipment, blood sugar monitors, walkers, and similar equipment
  • Ambulatory surgical center services

Preventive services: the part Medicare gets genuinely right

Most preventive services are covered at 100%, with no deductible and no copay, as long as your provider accepts Medicare assignment. This includes:

  • Your one-time “Welcome to Medicare” wellness visit, available within your first 12 months on Part B
  • Annual wellness visits after that
  • Flu shots and most other recommended vaccines
  • Mammograms
  • Colonoscopies and other cancer screenings
  • Diabetes and cardiovascular screenings
  • Many other screenings recommended by the U.S. Preventive Services Task Force

Paul’s Honest Take: This is one of the most underused parts of Medicare, full stop. I’ve had clients who paid for a private physical every year out of habit and never realized their annual wellness visit through Medicare was completely free. If you haven’t used your Welcome to Medicare visit or your annual wellness visit, that’s real value sitting on the table.

What’s NOT covered

  • Routine dental care — cleanings, fillings, dentures, extractions
  • Routine vision exams and eyeglasses
  • Hearing aids (though diagnostic hearing tests ordered by a doctor may be covered)
  • Long-term custodial nursing home care — help with daily living activities, as opposed to short-term skilled or medical care
  • Routine prescription drugs you pick up at a retail pharmacy — that’s Part D’s job, not Part B’s
  • Cosmetic surgery, unless medically necessary (such as reconstruction after an accident or mastectomy)
  • Most care received outside the United States, with very limited exceptions
  • Routine foot care, such as nail trimming, in the absence of a qualifying medical condition
  • Acupuncture, except for a narrow, specific chronic low back pain benefit
  • Concierge medicine fees and membership-style charges some practices add on top of standard care
  • Long-term care insurance-style services, including most home-based personal care that isn’t tied to a skilled medical need

Paul’s Honest Take: The dental and vision exclusions are the ones that surprise people most, especially since they’re such routine parts of healthcare for most adults. This is exactly why so many Medicare Advantage plans build dental, vision, and hearing benefits into their coverage — Original Medicare was simply never designed to include them, and that gap doesn’t go away on its own.

What Part B Costs in 2026

Part B has three separate cost components, and understanding all three matters:

Cost Component

2026 Amount

Standard monthly premium

$202.90

Annual deductible

$283

Coinsurance on most covered services

20%

The premium is deducted automatically from your Social Security check if you’re already collecting benefits. If you’re not yet collecting Social Security, you’ll receive a bill, typically every three months.

The deductible works differently than Part A’s — it’s a straightforward annual figure. You pay the first $283 of Medicare-approved outpatient costs each calendar year, and then Medicare’s cost-sharing kicks in.

The coinsurance is where the real risk lives. After your deductible is met, Medicare pays 80% of the Medicare-approved amount for most covered services, and you’re responsible for the remaining 20%. There is no yearly cap on this 20% under Original Medicare alone. If you have a $100,000 course of cancer treatment, your 20% share is $20,000 — unless you have a Medigap policy or Medicare Advantage plan absorbing that cost.

Paul’s Honest Take: I put this in bold because it’s genuinely the single most important number in this entire guide. That uncapped 20% is the whole reason Medigap and Medicare Advantage exist as products in the first place. Original Medicare by itself was never designed to protect you from a truly expensive year — it was designed to cover 80% of it and leave the rest to you.

IRMAA: What Higher Earners Actually Pay

If your income is above certain thresholds, you’ll pay more for Part B through the Income-Related Monthly Adjustment Amount (IRMAA) — based on your tax return from two years prior. For 2026, that means your 2024 income determines your premium tier.

2024 Income (Individual)

2024 Income (Married, Joint)

Total Part B / Month

$109,000 or less

$218,000 or less

$202.90

$109,001 – $137,000

$218,001 – $274,000

$284.10

$137,001 – $171,000

$274,001 – $342,000

$405.80

$171,001 – $205,000

$342,001 – $410,000

$527.50

$205,001 – $499,999

$410,001 – $749,999

$649.20

$500,000 and above

$750,000 and above

$689.90

At the top tier, you’re paying more than three times the standard premium. If your income has recently dropped — retirement, the loss of a spouse, or certain other life-changing events — you can appeal your IRMAA determination using Form SSA-44.

Do You Have to Enroll? And What Happens If You Don’t?

Technically, Part B is optional — Medicare won’t force you into it. But opting out without a valid alternative is genuinely risky, because of how the penalty structure works.

If you don’t sign up during your Initial Enrollment Period (the 7-month window around your 65th birthday) and you don’t have qualifying employer coverage, you’ll face a permanent 10% penalty added to your premium for every full 12-month period you went without Part B. That penalty doesn’t expire — you pay it for as long as you have Part B, which for most people means for the rest of your life.

Example: If you delayed enrollment by 24 full months without a valid exception, you’d pay an extra 20% on top of the standard $202.90 premium in 2026 — roughly $40.58 more, every month, permanently.

How Part B Works with Group Insurance

Just like Part A, whether you can safely delay Part B without penalty comes down to one specific number: how many employees your company has.

Companies with 20 or more employees: If you or your spouse are actively working and covered by a genuine group health plan, your workplace insurance is primary, and you can legally delay Part B without any penalty. When that employment or coverage eventually ends, you get an 8-month Special Enrollment Period to enroll in Part B penalty-free.

Companies with fewer than 20 employees: Medicare automatically becomes your primary insurer at 65, regardless of your employment status. You need to enroll in Part B right on schedule. If you don’t, your small employer’s plan can legally refuse to pay claims that Medicare should have covered first — potentially leaving you responsible for the full cost.

Paul’s Honest Take: I say this in nearly every guide I write, because it’s genuinely one of the costliest misunderstandings I encounter: “I have good coverage at work” and “I’m protected from Medicare’s enrollment deadlines” are two completely different statements, and whether the second one is true depends entirely on your employer’s size — not how generous the coverage feels. Confirm the actual employee count before you decide to delay anything.

Retiree Coverage Is Not the Same as Active Employer Coverage

This is a distinction that catches a genuinely large number of people off guard: the “20 or more employees” exception only applies to active employment. If you retire and your former employer offers you retiree health benefits — sometimes a genuinely good, comprehensive plan — that coverage does not create a Special Enrollment Period the way active group coverage does, and it does not exempt you from enrolling in Part B on time.

Paul’s Honest Take: I’ve seen this mistake more than once, and it’s an especially painful one because it happens to people who did everything right during their working years. Someone retires with a strong retiree health plan from a large employer, assumes it works the same way their active coverage did, and delays Part B — only to find out later that retiree coverage was never a valid reason to delay in the first place. The moment you stop actively working, that clock starts, regardless of how good your retiree plan looks on paper. If you’re retiring and keeping employer retiree benefits, treat enrolling in Part B as something to handle right on schedule, not something retiree coverage lets you postpone.

Why You Need Both Part A and Part B for Medigap or Medicare Advantage

Here’s a foundational requirement worth understanding clearly, since it shapes every other coverage decision in Medicare: you must be enrolled in both Part A and Part B before you can buy a Medigap policy or enroll in a Medicare Advantage plan. Neither product exists as a standalone substitute for Original Medicare — both are built specifically to work alongside it.

  • Medigap fills the cost-sharing gaps left by Original Medicare (Parts A and B) — it has nothing to fill in if you’re not enrolled in both parts to begin with.
  • Medicare Advantage legally must provide at least the same coverage as Parts A and B combined, which is only possible because you’re required to be enrolled in both before a Medicare Advantage carrier can enroll you.

Paul’s Honest Take: This surprises people who assume they can somehow “skip” Part B and go straight into a Medicare Advantage plan to avoid the extra premium. It doesn’t work that way — Part B enrollment, and its premium, is a prerequisite either way, whether you end up on Original Medicare with Medigap or on a Medicare Advantage plan. There’s no path through Medicare that avoids the Part B premium once you’re actually using the system.

Does Medicare Work If You’re a Veteran?

Yes — and if you have VA health benefits, understanding how the two systems relate is genuinely important, because they work differently than most people assume.

Medicare and VA benefits do not coordinate. These are two entirely separate systems that each pay only for care received within their own network. Medicare doesn’t pay for care you receive at a VA facility, and VA benefits don’t pay for care you receive from a non-VA doctor or hospital. You, the veteran, choose which system to use each time you seek care.

Here’s the critical point: having VA benefits does not exempt you from Medicare’s enrollment deadlines. VA coverage is not considered a qualifying reason to delay Part B without penalty. If you don’t enroll in Part B during your Initial Enrollment Period and you’re relying solely on VA benefits, you can still trigger the permanent late enrollment penalty.

Why the VA itself recommends enrolling in Medicare anyway:

  • It gives you access to civilian doctors and hospitals outside the VA system
  • VA healthcare funding depends on annual Congressional appropriations, which isn’t guaranteed to remain stable
  • If VA authorizes only part of your needed care at a non-VA facility, Medicare can help cover the rest
  • Having both gives you meaningfully more flexibility and security than relying on either system alone

Paul’s Honest Take: This is one of the most common misconceptions I run into with veterans specifically, and it’s an expensive one to get wrong. Good VA coverage feels like it should be enough, and it might genuinely handle most of your care — but it doesn’t protect you from the Part B enrollment clock the way employer coverage from a large company can. The VA itself actively encourages enrolling in Medicare Parts A and B for exactly this reason. If you have VA benefits and are approaching 65, this is worth a direct conversation before you assume you’re covered.

Veterans who enroll in Part B can also purchase a Medigap policy, which can be particularly valuable if you use non-VA providers regularly — though if you primarily rely on VA facilities for most of your care, the value of an added Medigap policy may be more limited, and worth weighing carefully.

How Long Does It Actually Take to Get Part B Approved?

This is one of the most practical, and most overlooked, pieces of planning — especially if you’re leaving a job after 65 and coordinating your Part B start date around the end of your employer coverage. Applying isn’t instant, and the timeline depends heavily on which enrollment window you’re using.

Enrollment Situation

Typical Processing Time

When Coverage Actually Starts

Initial Enrollment Period (around 65)

2–4 weeks, sometimes up to 6

1st of your birthday month (if applied in the 3 months before) or 1st of the month after you apply (if applied during or after your birthday month)

Special Enrollment Period (leaving employer coverage)

4–8 weeks, sometimes longer

1st of the month after your application is submitted

General Enrollment Period (Jan 1–Mar 31, missed window)

4–6 weeks

1st of the month after you apply

Why the Special Enrollment Period takes longer: applying after leaving employer coverage requires two forms, not one — Form CMS-40B (the actual Part B application) and Form CMS-L564 (Request for Employment Information), which your employer needs to complete to verify you had qualifying coverage. Social Security has to manually review both, which is exactly why this route consistently takes longer than a standard Initial Enrollment Period application.

Paul’s Honest Take: This timeline question comes up constantly with clients who are retiring or leaving a job after 65, and it deserves real attention — not just because of the penalty risk we’ve already covered, but because a slow approval can leave you with an actual gap in coverage if you time it too tightly. My standard advice: start this process at least 2 to 3 months before you need Part B to actually begin, not the week your employer coverage ends. If your former employer is slow to complete their portion of Form CMS-L564, that alone can hold up the entire application — so it’s worth following up with your HR or benefits department directly rather than assuming it’s been submitted.

Practical tips to avoid delays

  • Apply online through SSA.gov whenever possible. It’s consistently the fastest method — mailed or faxed forms are more prone to getting lost or delayed.
  • If you’re on a Special Enrollment Period, submit Form CMS-L564 alongside Form CMS-40B, not separately. They need to arrive together, and one incomplete form can stall the whole application.
  • Expect a short intake lag even with online applications. It can take several business days for an online submission to actually appear on a local Social Security agent’s screen — don’t panic if you call shortly after applying and they say they don’t see it yet.
  • Once approved, you don’t have to wait for your physical card. Your Medicare Beneficiary Identifier typically appears in your online Social Security or Medicare.gov account within a day or two of approval, and you can print a temporary card from there — the physical card generally arrives by mail within about 30 days.

Excess Charges: The Cost Almost Nobody Knows to Ask About

Here’s a detail that surprises even people who’ve been on Medicare for years: not every doctor who accepts Medicare agrees to accept Medicare’s approved amount as full payment.

Providers fall into three categories:

  • Participating providers accept Medicare assignment, meaning they agree to accept the Medicare-approved amount as payment in full. This covers the vast majority of providers — roughly 98% of doctors nationally.
  • Non-participating providers still accept Medicare patients but haven’t agreed to accept the standard rate. They can charge an excess charge of up to 15% above the Medicare-approved amount.
  • Opted-out providers have left the Medicare system entirely and can charge whatever they want under a private contract — Medicare pays nothing at all for care from these providers, except in emergencies.

How excess charges actually work: if the Medicare-approved amount for a service is $300 and you see a non-participating provider, they can legally charge up to an additional $45 (15%) on top, for a total bill of $345 — and that excess amount doesn’t count toward your Part B deductible.

Eight states currently prohibit or limit excess charges entirely: Connecticut, Massachusetts, Minnesota, New York, Ohio, Pennsylvania, Rhode Island, and Vermont. If you live in one of these states, you’re generally shielded from excess charges from providers within your state — though you could still face them if you receive care from a non-participating provider elsewhere.

Paul’s Honest Take: This is exactly why Medigap Plan G matters so much for people who want maximum flexibility. Plan G covers excess charges in full — Plan N does not. If you’re the kind of person who wants the freedom to see any doctor without worrying about billing surprises, that distinction is worth understanding clearly before you pick between the two. And regardless of which plan you choose, it’s always worth asking a new provider directly whether they accept Medicare assignment before your first appointment.

The HSA Rule: Part B Closes the Door Too

If you’re hoping to keep contributing to a Health Savings Account, know this clearly: enrolling in Part B — or any part of Medicare — ends your ability to make new HSA contributions. This isn’t unique to Part B; it applies the moment you enroll in Medicare in any form, including premium-free Part A.

If keeping your HSA active matters to you, the only way to legally delay both Part A and Part B is through qualifying employer coverage — which, as covered above, generally requires an employer with 20 or more employees. And because Part A enrollment can be backdated up to 6 months once you do enroll, it’s smart to stop HSA contributions 6 months before you plan to sign up for Medicare or file for Social Security, whichever comes first.

Frequently Asked Questions

Is there a cap on what I’ll pay for Part B services in a year? Not under Original Medicare alone — the 20% coinsurance has no yearly limit. A Medigap policy or Medicare Advantage plan is what actually caps your exposure.

What happens if I don’t sign up for Part B on time? You’ll generally face a permanent 10% penalty on your premium for every 12-month period you went without coverage, unless you qualify for a Special Enrollment Period through active employer coverage.

Do I need Part B if I have good coverage through a small employer? Almost certainly yes. If your employer has fewer than 20 employees, Medicare becomes your primary insurer at 65 regardless of your job coverage, and not enrolling can leave you exposed to unpaid claims and a lifelong penalty.

Do veterans need Medicare Part B if they have VA benefits? Generally, yes. Medicare and VA benefits don’t coordinate — each only pays for care within its own system — and VA coverage doesn’t exempt you from Medicare’s enrollment deadlines or penalties.

What is a Part B excess charge? An additional charge, up to 15% above the Medicare-approved amount, that a non-participating provider can legally bill you. It doesn’t count toward your deductible, and only Medigap Plan G (among current plans) covers it in full.

Can I keep contributing to my HSA if I enroll in Part B? No. Enrolling in any part of Medicare, including Part B, ends your HSA contribution eligibility going forward.

How long does it take to get approved for Part B? It depends on the enrollment window. Initial Enrollment Period applications typically process in 2–4 weeks. Special Enrollment Period applications, used when leaving employer coverage, generally take 4–8 weeks since Social Security must manually verify your prior coverage using Form CMS-L564. Start the process at least 2–3 months before you need coverage to begin, especially when coordinating around a job ending.

The Bottom Line

Part B is the half of Medicare that covers your everyday medical care — and it’s also where the real financial exposure of Original Medicare lives, thanks to that uncapped 20% coinsurance. Whether you should enroll at 65, whether you can safely delay, and how much of that exposure you’re carrying all depend on details specific to your situation: your employer’s size, your income, your VA status, and which doctors you actually see.

If you want help sorting out exactly how Part B applies to your specific circumstances — or want to understand how Medigap or Medicare Advantage could close that uncapped coinsurance gap — that’s exactly the conversation I have with clients every day, at no cost to you.

Call 631-358-5793 or visit paulbinsurance.com to set up a time to talk it through.

Paul Barrett, CMIP, is the founder of The Modern Medicare Agency, based in Melville, NY, and has spent 18+ years exclusively helping people navigate Medicare — never life insurance, never annuities, just Medicare. He’s licensed in 37 states, represents more than 40 carriers, and has personally helped over 5,000 clients choose coverage that actually fits their lives.

Figures current as of 2026 and sourced from CMS, Medicare.gov, and the Social Security Administration. Individual circumstances vary, especially around employer coverage, VA benefits, and income-based premiums — always verify your specific situation before making enrollment decisions.

Sources

Related Post

Scroll to Top

